
PMS Symptoms Across Menstrual Cycle
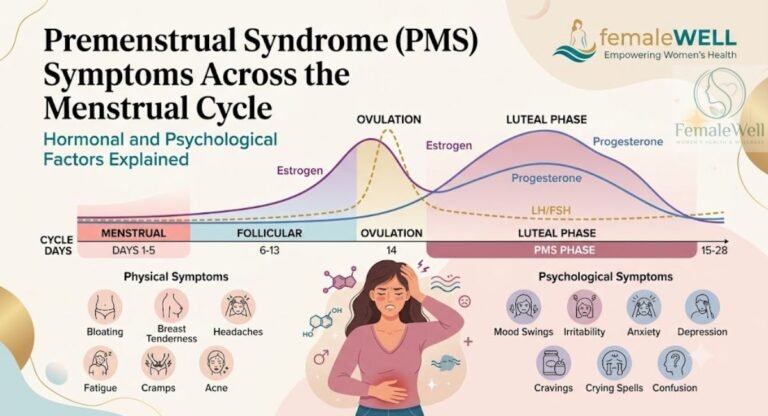
Premenstrual Syndrome (PMS) Symptoms Across the Menstrual Cycle: Hormonal and Psychological Factors Explained
Understand how estrogen, progesterone, and neurotransmitters drive physical and emotional changes throughout your monthly cycle—backed by medical expert insight.
- Cycle Dynamics: How hormone fluctuations shift across Follicular, Ovulatory, and Luteal phases.
- Physical vs. Emotional: Identifying root causes behind bloating, cramps, anxiety, and mood swings.
- Science-Backed Relief: Doctor-approved strategies to stabilize mood and balance cycle symptoms.
For many women, the days before menstruation can bring a noticeable shift in how the body and mind feel. Premenstrual Syndrome (PMS) symptoms may include breast tenderness, bloating, headaches, fatigue, food cravings, irritability, anxiety and changes in mood. These symptoms often follow a recurring pattern during the menstrual cycle, particularly during the luteal phase after ovulation. However, PMS is not simply a matter of having “too many” or “too few” hormones. Research suggests that some people may be more sensitive to normal fluctuations in estrogen, progesterone and related neuroactive compounds.
At the same time, psychological factors, stress, sleep quality and emotional wellbeing can influence how symptoms are experienced. Understanding these interactions can help you recognize your personal pattern and distinguish typical PMS from more severe conditions such as PMDD. This guide explores the hormonal and psychological factors behind PMS symptoms across the menstrual cycle.
What Is Premenstrual Syndrome (PMS)?
PMS describes a recurring collection of physical, emotional and behavioral symptoms that appear in relation to the menstrual cycle. Common experiences include mood changes, irritability, anxiety, tiredness, headaches, bloating, breast tenderness, appetite changes and sleep problems. Importantly, symptoms vary between people and can change from one cycle to another. What makes PMS different from an occasional difficult day is its cyclical pattern. Symptoms tend to emerge during the premenstrual phase and improve around or after menstrual onset. This timing matters because headaches, low mood or fatigue that remain present throughout the month may have another explanation. A symptom diary can therefore reveal more than a single blood test ever could.
When Do PMS Symptoms Usually Begin?
The days leading up to menstruation are the period most commonly associated with PMS. NHS guidance notes that symptoms can start or intensify during the two weeks before a period and usually ease after menstruation begins. The exact timing varies because ovulation and cycle length differ between individuals.
How PMS Differs From Normal Menstrual Changes
Normal menstrual cycle phases involve substantial biological changes. Those changes do not automatically represent a disorder. PMS becomes more relevant when recurring symptoms cause noticeable distress or interfere with daily functioning. In other words, feeling slightly tired before your period is not the same clinical situation as repeatedly being unable to work because of severe mood or physical symptoms.
PMS vs. Premenstrual Dysphoric Disorder (PMDD)
PMS and premenstrual dysphoric disorder exist on a related spectrum but are not interchangeable terms. PMDD involves more severe symptoms, particularly mood-related symptoms such as marked irritability, anxiety, or depressed mood. The symptoms can significantly affect relationships, work, and social functioning. NHS guidance also emphasizes the importance of seeking help when PMDD symptoms become severe.
| Feature | PMS | PMDD |
|---|---|---|
| Physical symptoms | Common | Common |
| Emotional symptoms | Possible | Often prominent |
| Symptom severity | Variable | Often severe |
| Daily functioning | May be affected | Frequently affected |
| Cyclical timing | Important | Essential |
| Clinical assessment | Symptom history and pattern | Prospective symptom assessment is particularly important |
Understanding the Clinical Threshold
The dividing line is not simply whether someone feels miserable before menstruation. Clinicians consider the number and type of symptoms, their symptom timing, severity, and impact on everyday life. PMDD diagnostic criteria place particular emphasis on recurring affective symptoms and functional impairment.
How PMS Symptoms Change Throughout the Menstrual Cycle
Think of the menstrual cycle phases as a moving biological landscape rather than four rigid boxes. Estrogen, progesterone and other reproductive signals rise and fall in sequence. Meanwhile, your brain, metabolism, sleep, appetite and emotional systems respond to those changes. This is why symptoms across the menstrual cycle can look completely different from one phase to another.
For someone with PMS, the most noticeable changes often occur after ovulation and during the late luteal phase. Yet symptoms do not always wait until the final few days. Some people notice early luteal changes while others experience a sharper shift closer to menstrual onset. Research therefore focuses heavily on menstrual cycle timing rather than assuming every person follows the same calendar.
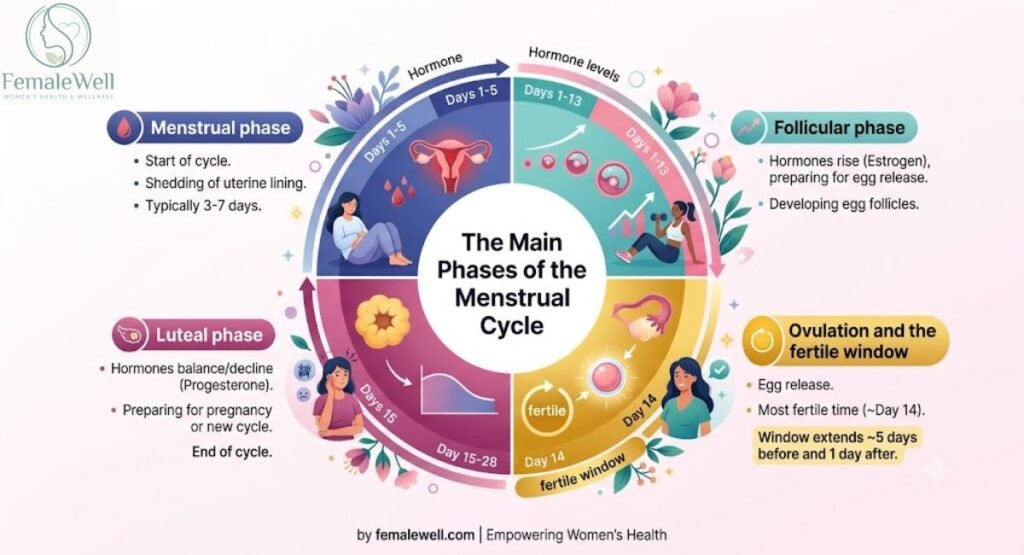
The Main Phases of the Menstrual Cycle
The classic cycle includes menstruation, the follicular phase, ovulation and the luteal phase. Each stage has its own hormonal environment. Understanding those transitions makes it easier to see why late-cycle symptoms can emerge after a relatively symptom-free period earlier in the cycle.
Menstrual phase
The menstrual phase begins on the first day of menstrual bleeding. Ovarian hormone levels have fallen after the previous cycle failed to result in pregnancy. Cramps, fatigue, headaches and other menstrual symptoms may occur here, but symptoms caused by menstruation should not automatically be labeled PMS.
Follicular phase
During the follicular phase, ovarian follicles develop and estradiol generally rises as the body prepares for ovulation. Many people report fewer premenstrual symptoms during this part of the cycle. However, individual experiences vary, and the absence of PMS-type symptoms does not mean that every person feels physically or emotionally identical during the follicular phase.
Ovulation and the fertile window
Ovulation marks a major turning point in the ovulatory cycle. A rise in luteinizing hormone, commonly called the LH surge, triggers ovulation. The fertile window surrounds this event because sperm can survive for several days while the egg remains viable for a shorter period. Some people also notice mild mid-cycle abdominal pain, known as mittelschmerz.
Luteal phase
After ovulation, the corpus luteum produces progesterone. This creates the hormonal environment of the luteal phase. Progesterone rises and later falls if pregnancy does not occur. For people who experience PMS, this post-ovulatory period is especially important because symptoms can emerge during the luteal phase and become stronger as menstruation approaches.
When PMS Symptoms Typically Emerge
The exact PMS symptom emergence point differs from person to person. Some individuals notice changes soon after ovulation, while others remain comfortable until the final days of the cycle. Research describes early, middle, and late luteal patterns rather than one universal starting day.
Why Symptoms Increase Before Menstruation
The days before menstrual onset involve a changing endocrine environment. Progesterone and its neuroactive metabolites decline after reaching their luteal peak, alongside changes in estradiol.
In susceptible individuals, these transitions influence brain pathways involved in mood, sleep, appetite, and emotional regulation—even when hormone concentrations are clinically normal.
What Happens When Menstruation Begins?
For many people, PMS symptoms decrease noticeably once menstruation begins. NHS guidance describes symptoms as generally easing after the period starts.
Hormonal Factors & PMS Symptom Dynamics
Comparative analysis showing how central nervous system sensitivity amplifies premenstrual symptoms compared to absolute blood hormone levels.
Neuro-Hormonal Impact Scale
Are Symptoms Caused by High or Low Levels?
No. Research confirms that individuals with severe PMS rarely have abnormally high or low concentrations of estrogen or progesterone. Their endocrine serum levels mirror those without PMS symptoms.
Why Hormone Sensitivity Matters More
It is the brain’s unique molecular sensitivity to normal hormonal declines (particularly allopregnanolone drops) that triggers serotonin dysregulation, mood changes, anxiety, and fluid retention.
Psychological Factors That May Influence PMS
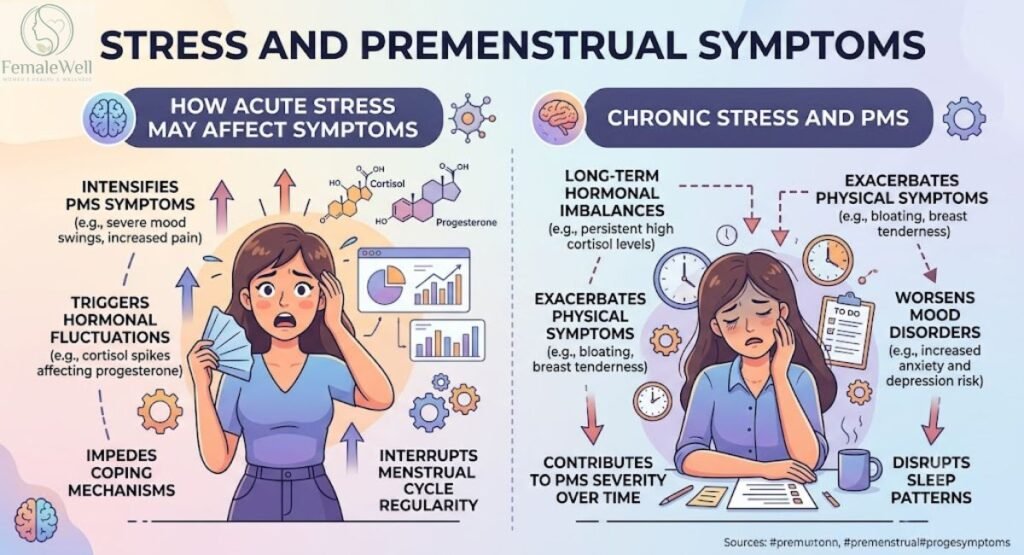
PMS is not imaginary and it is not simply a problem of attitude. At the same time, psychological factors can influence how symptoms develop and how strongly they are experienced. Stress, sleep quality, anxiety, emotional regulation and social pressures can interact with biological changes. The result is a genuine brain-body experience that cannot be neatly separated into “physical” and “psychological” boxes.
The modern view is therefore biopsychosocial. Psychological predictors of PMS do not replace hormonal explanations. Instead, they may modify symptom expression. Someone facing chronic work pressure, poor sleep and relationship conflict may experience a different premenstrual month from the same person during a calm period. Research increasingly examines these individual differences rather than searching for one universal PMS mechanism.
Psychological Factors & PMS
How brain neurochemistry, personality traits, sleep, and stress shape premenstrual emotional and physical health.
Anxiety & Mood Changes
Luteal drops in progesterone and serotonin alter brain circuit reactivity, triggering sudden anxiety, mood swings, and emotional sensitivity before menses.
Neuroticism & Sensitivity
Individual traits like higher stress sensitivity or neuroticism lower emotional resilience, making normal premenstrual shifts feel noticeably more severe.
Sleep & Emotional Health
Progesterone shifts disrupt REM and deep sleep during the luteal phase. Poor sleep directly worsens emotional instability and daytime irritability.
Stress & Physical Link
Psychological stress amplifies central pain pathways—turning internal stress directly into heightened cramps, tension headaches, and fatigue.
Common PMS Symptoms and When They Appear
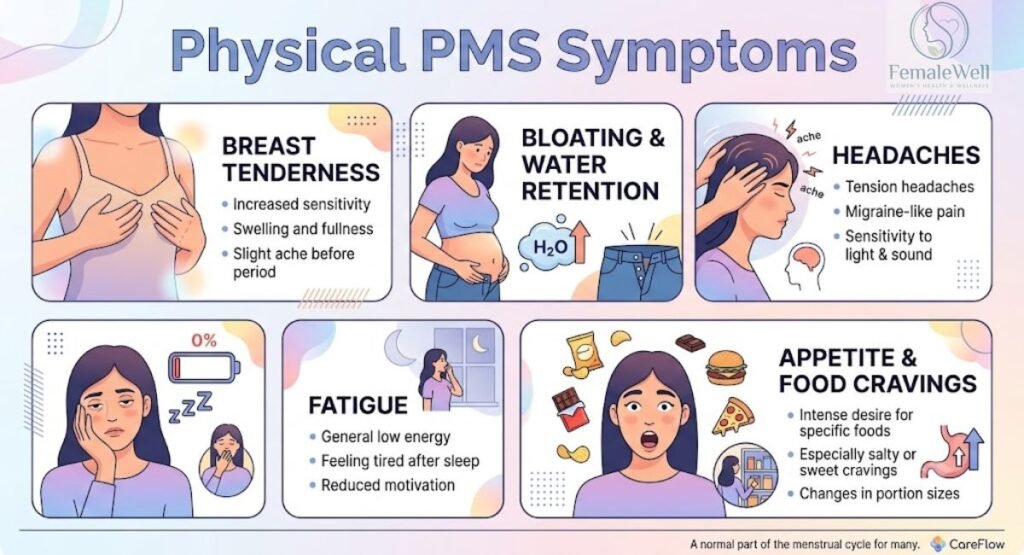
PMS can feel like a collection of unrelated problems until you place them on a timeline. Breast tenderness may appear alongside bloating. Fatigue may arrive with irritability. Food cravings may accompany poor sleep. These combinations are not unusual. NHS guidance lists mood changes, anxiety, tiredness, bloating, breast tenderness, headaches and appetite changes among common PMS experiences.
The important clue is not whether you recognize one symptom. It is whether several cyclical symptoms repeatedly follow a similar pattern. Your symptom profile may also change over time. One month may bring headaches and breast tenderness while another produces more emotional symptoms. That cycle-to-cycle variability does not automatically mean the pattern is unrelated to menstruation.
Emotional and Psychological Symptoms
PMS mood shifts affect relationships and self-perception. Their key indicator is cyclicity: appearing premenstrually and receding after menses.
Irritability & Mood Swings
A shorter fuse where small frustrations feel overwhelming. Tracking helps distinguish recurring luteal conflict from general stress.
Anxiety & Worry
Premenstrual restlessness or feeling unable to cope. If anxiety persists all month, assess for a general anxiety disorder.
Low Mood & Feeling Flat
Temporary emotional flatness. Diagnostic certainty depends on confirming a clear, symptom-free period post-menstruation.
Concentration & Brain Fog
Focus difficulties driven by poor luteal sleep and fatigue. Record alongside sleep and mood rather than as an isolated effect.
How to Track PMS Symptoms and Identify Your Personal Pattern
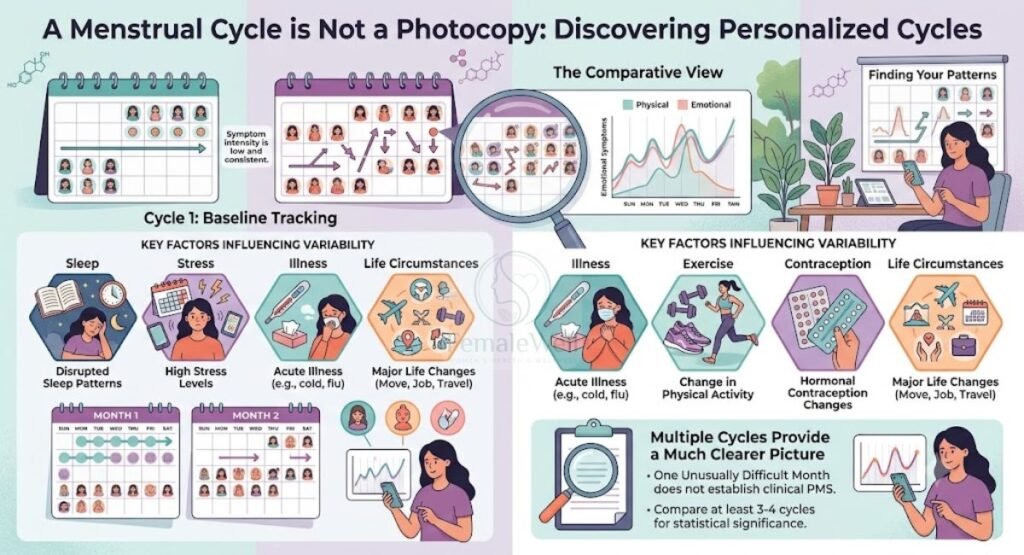
If you want to understand your own PMS pattern, start with observation rather than guesswork. PMS symptom tracking can show whether symptoms reliably appear during the same portion of the cycle. It can also reveal something equally important: perhaps a symptom you blamed on PMS actually persists throughout the month.
A simple daily record can become valuable clinical evidence. NHS guidance recommends keeping a symptom diary for at least two menstrual cycles when assessing PMS or PMDD. The goal is not to become obsessed with every sensation. Instead, you are creating a timeline that makes otherwise invisible cyclical changes easier to recognize.
What to Track During Each Menstrual Cycle
Key parameters to log consistently for establishing clinical cyclicity and identifying PMS/PMDD patterns.
When PMS Symptoms May Require Medical Evaluation
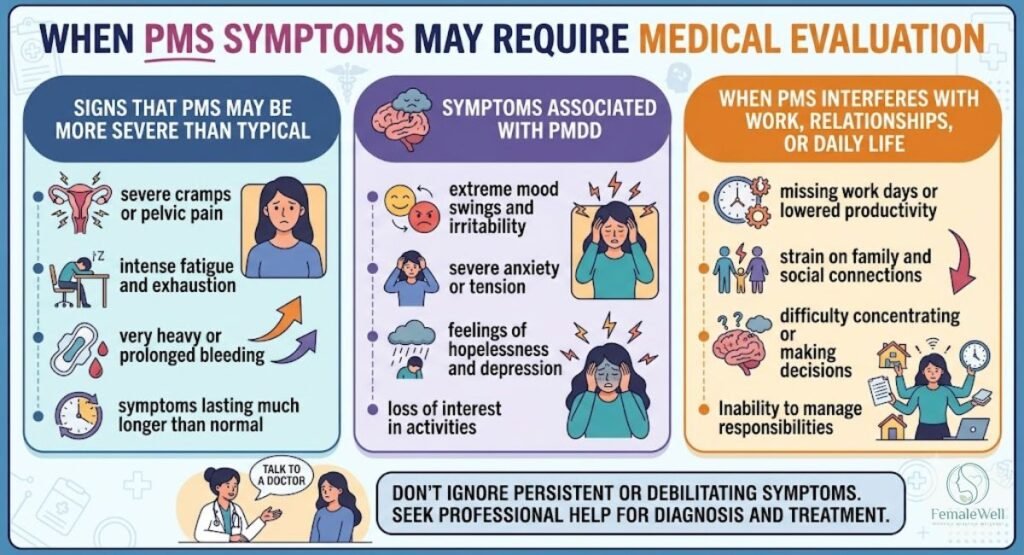
PMS deserves medical attention when it repeatedly interferes with your life. You should not have to accept severe symptoms as something you simply need to endure because they happen every month. Clinical PMS can affect work, relationships and wellbeing, while PMDD can produce substantial emotional impairment. Effective assessment begins by understanding the pattern rather than dismissing the symptoms.
Medical evaluation becomes particularly important when symptoms are severe, new, progressively worsening or present outside the expected premenstrual window. Persistent fatigue, depression, anxiety, pain or abnormal bleeding may have causes unrelated to PMS. A clinician can consider the menstrual pattern alongside your broader reproductive and general health.
What a Healthcare Professional May Evaluate
Assessment usually begins with your symptom history and menstrual pattern. A clinician may also consider medications, contraception, mental health, sleep, stress, and other medical conditions. Prospective symptom records can make this conversation much more productive because they show menstrual timing rather than relying entirely on memory.
Prospective Symptom Severity Across a 28-Day Cycle
A visual representation of how symptom tracking pinpoints PMS/PMDD timing relative to menstruation.
Note: Notice how severe symptoms peak sharply during the luteal phase and resolve abruptly with the onset of menstruation (Day 1).
Menstrual and Symptom History
Your clinician may ask when symptoms start, how long they last, and whether they disappear after menstruation. They may also ask about cycle length, bleeding, and the number of symptom-free days. A prospective diary can help establish whether your symptoms meet a recognizable pattern of clinical-level symptoms.
Mental Health and Stress Factors
A clinician may ask about anxiety, depression, sleep, work pressure, and relationship stress. This does not mean your symptoms are being dismissed as psychological. Instead, these questions help identify psychosocial factors that may intensify symptoms or reveal a condition that deserves separate treatment.
Possible Underlying Conditions
Symptoms that resemble PMS can occur with other conditions. Depending on your history, a clinician may consider thyroid disorders, migraine, anemia, endometriosis, adenomyosis, depression, anxiety disorders, or perimenopause. The aim is not to find another diagnosis at all costs. It is to avoid assuming that every recurring symptom is automatically PMS.
Questions to Ask Your Doctor About Persistent Premenstrual Symptoms
A useful medical conversation can begin with simple questions. Bringing several months of records can make these questions far easier to answer:
- Is my symptom pattern consistent with standard PMS or PMDD?
- Would prospective tracking for 2–3 months provide clearer diagnostic insight?
- Could another underlying medical condition explain or exacerbate my symptoms?
- How might my current medications or contraception options influence this pattern?
FAQs About PMS and Hormones
Understanding PMS becomes easier when the most common questions have straightforward answers. The central theme remains the same: symptom timing matters. Hormonal fluctuations provide the biological backdrop, but individual sensitivity and psychological context help shape what you actually experience.
There is no universal PMS day because menstrual cycles and ovulation timing differ. Symptoms commonly develop during the luteal phase and may become stronger during the days before menstrual onset. NHS guidance notes that PMS symptoms can occur during the two weeks before a period. Tracking your own cycle is more informative than relying on one fixed calendar day.
No single hormone explains every case. Hormones and PMS are connected through changes in estrogen, progesterone and neuroactive steroid pathways. Current research increasingly emphasizes sensitivity to hormonal fluctuations rather than simply having an abnormally high or low hormone concentration.
Stress can interact with PMS symptoms, although the relationship is not a simple cause-and-effect equation. Higher momentary stress levels, poor sleep and emotional strain can affect pain, mood and coping. Research into PMDD also suggests that altered luteal-phase stress sensitivity may involve interactions between neuroactive steroids and the HPA axis.
Yes. Symptoms can appear during the early luteal phase after ovulation, although many people notice stronger symptoms later. Research has reported early, middle and late luteal symptom emergence. Therefore, symptoms after ovulation can still fit a premenstrual pattern when they consistently resolve around menstruation.
Your body does not repeat every cycle under identical conditions. Daily stressors, sleep, illness, lifestyle, hormonal contraception and cycle timing can all influence symptom experience. Biological sensitivity may also vary. Tracking multiple cycles can reveal whether differences represent ordinary variation or a meaningful change in your usual pattern.
Yes. Having normal hormone levels does not rule out PMS. The problem may involve how the brain responds to ordinary hormone fluctuations and mood rather than an endocrine abnormality. Research on PMDD particularly emphasizes altered sensitivity to neuroactive steroids and their effects on GABA-related brain pathways.
PMS can involve physical and emotional symptoms that vary in severity. PMS and PMDD differ mainly in severity, symptom profile and functional impact. PMDD is characterized by prominent and clinically significant mood symptoms that recur in relation to the menstrual cycle. If symptoms substantially affect your life, professional assessment is appropriate.
The strongest practical clue is repetition. Record symptoms every day across at least two cycles and compare them with ovulation and menstrual timing where possible. If symptoms repeatedly appear during the same premenstrual period and then improve after menstruation, that provides evidence of a cyclical relationship. NHS guidance recommends symptom diaries as part of PMDD assessment.