Signs Perimenopause Is Ending: What to Expect in the Final Stages
Recognize late-stage perimenopause symptoms, understand cycle changes, and prepare transitionally into menopause with clinical clarity and expert guidance.
DK
Medically Reviewed byDr. KanzaWomen’s Health Expert
Published on femalewell.com
Key Highlights at a Glance
Longer Gaps Between Periods: Skipping 60+ consecutive days marks late perimenopause.
Symptom Shifts: Hot flashes may intensify while breast tenderness and PMS lessen.
The 12-Month Rule: Menopause is officially diagnosed after 12 full months without a period.
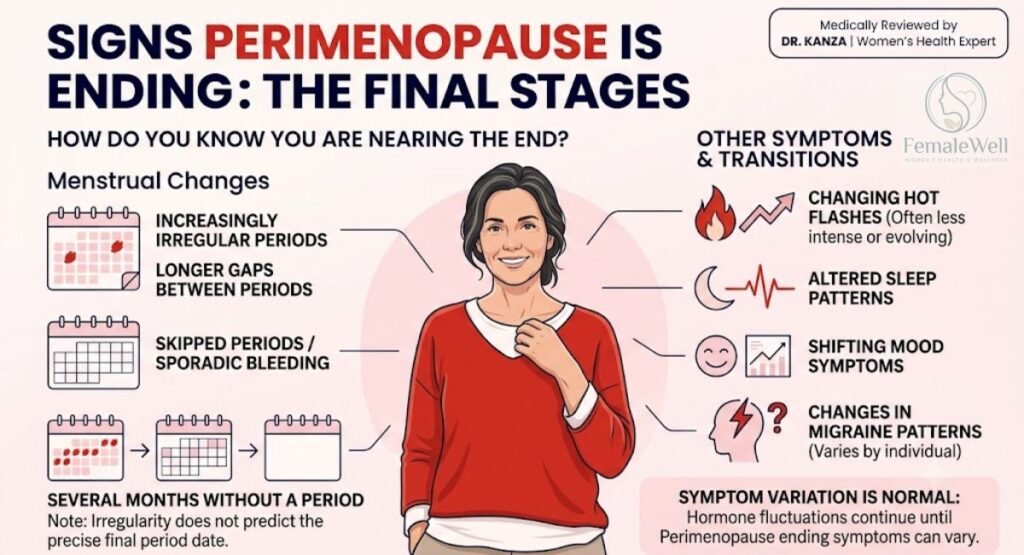
The signs perimenopause is ending can feel confusing because the final part of the menopause transition rarely follows a neat schedule. Your periods may become farther apart, hot flashes may change and sleep or mood symptoms may shift. Some symptoms can even disappear for weeks before returning. The final stage of perimenopause is the period leading toward your final menstrual period. During this late stage, hormone levels continue to change. Eventually, menstruation stops for good. However, you cannot usually predict the exact month when menopause will occur simply by looking at your symptoms.
Understanding Perimenopause and Its Final Stage
Perimenopause is the period surrounding the transition toward menopause. During the early stage, menstrual cycles may change subtly. You might notice shorter or longer cycles, heavier or lighter bleeding or an occasional missed period. As the transition progresses, periods often become more unpredictable and the gaps between them can become longer.
During late perimenopause, ovarian hormone production becomes increasingly irregular. Estrogen, also called oestrogen, does not simply fall in a smooth line. Instead, fluctuating estrogen, changing progesterone and other hormonal fluctuations can produce symptoms that appear, disappear or change intensity. The Menopause Society notes that late transition may involve skipped periods lasting 60 days or more.
How Do You Know You Are Nearing the End of Perimenopause?
One of the clearest signs perimenopause is coming to an end is a noticeable change in your menstrual pattern. Periods may become increasingly irregular with longer gaps between periods. You may experience skipped periods, sporadic bleeding or several months without a period. However, these changes alone cannot tell you exactly when your final period will occur.
Other perimenopause ending symptoms may include changing hot flashes, altered sleep, shifting mood symptoms and changes in migraine patterns. Some women notice that certain symptoms become less intense while others continue. This variation is normal because hormone fluctuations can continue until menopause is established.
Clinical Overview
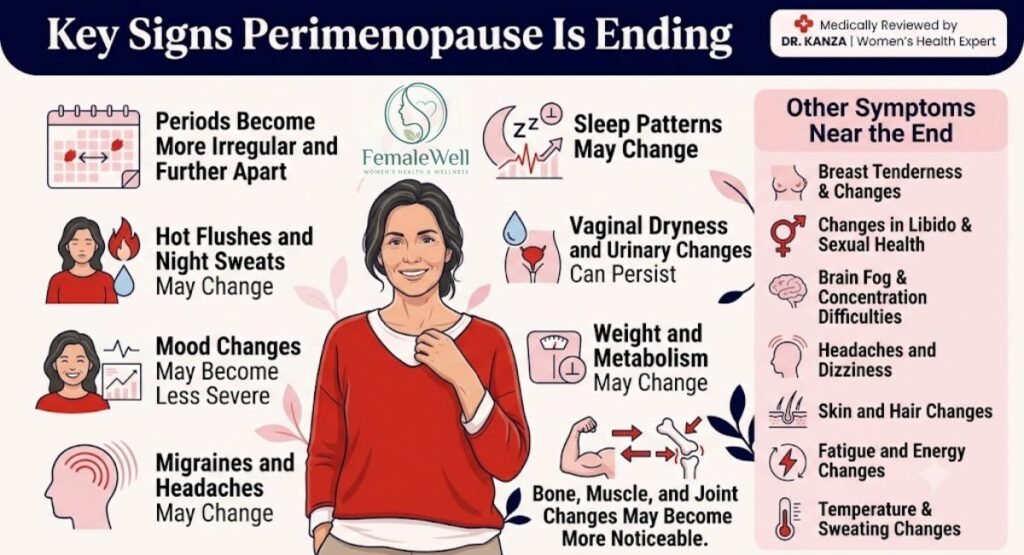
Key Signs Perimenopause Is Ending
As you enter the final stages of the transition, your body signals shifting hormone levels in distinct ways. Here is what to expect during late-stage perimenopause.
Filter by type:
01
Your Periods Become More Irregular and Further Apart
One of the strongest signs perimenopause is ending is a growing distance between menstrual periods. You may have a period one month and then wait several months for the next. Bleeding may also become lighter, shorter, heavier or less predictable.
Clinical Takeaway: The Menopause Society describes increasingly long gaps (such as 60+ days) as a characteristic hallmark feature of the late transition.
02
Hot Flushes and Night Sweats May Change
Hot flushes, known as hot flashes in the United States, are common vasomotor symptoms during the menopause transition. You may notice that they become less frequent or less intense as you approach or move beyond menopause.
Important Note: Vasomotor symptoms can continue for several years post-transition; their total disappearance alone is not a definitive marker.
03
Mood Changes May Become Less Severe
Mood swings, anxiety, irritability and low mood can occur during perimenopause. For some women, these symptoms become less severe as hormone fluctuations settle. For others, emotional symptoms may continue beyond the final period.
Holistic Insight: Mental health is influenced by hormone levels, sleep, stress, and lifestyle. Persistent depression always deserves expert medical evaluation.
04
Migraines and Headaches May Change
Hormonal migraines can become more frequent during perimenopause because fluctuating estrogen directly impacts headache patterns. Some women find that migraine symptoms improve once menstruation stops, while others continue having headaches.
Key Takeaway: A shift in migraine frequency is a recognized indicator of hormonal transition, but cannot establish menopause on its own.
05
Sleep Patterns May Change
Sleep can become unpredictable during the final stages. Night sweats, anxiety, temperature spikes, and frequent awakenings disrupt rest. Later, sleep quality may improve as vasomotor symptoms diminish.
Long-Term Care: Insomnia and nighttime waking can persist past menopause if tied to secondary health or lifestyle factors.
06
Vaginal Dryness & Urinary Changes Can Persist
Not every symptom fades when periods stop. Vaginal dryness, irritation, painful intercourse, and bladder symptoms (urgency, frequency, nighttime leaks, or recurrent UTIs) often become more noticeable as estrogen drops.
Treatable Condition: Known clinically as Genitourinary Syndrome of Menopause (GSM), highly effective clinical options are available.
07
Weight and Metabolism May Change
Changes in body composition become more pronounced during the transition. Weight gain, particularly around the abdomen, occurs alongside shifts in metabolism, physical activity, sleep patterns, and body fat distribution.
Declining ovarian estrogen accelerates changes in bone density and bone turnover. Many women also experience joint stiffness, joint discomfort, or changes in overall muscular strength during this period.
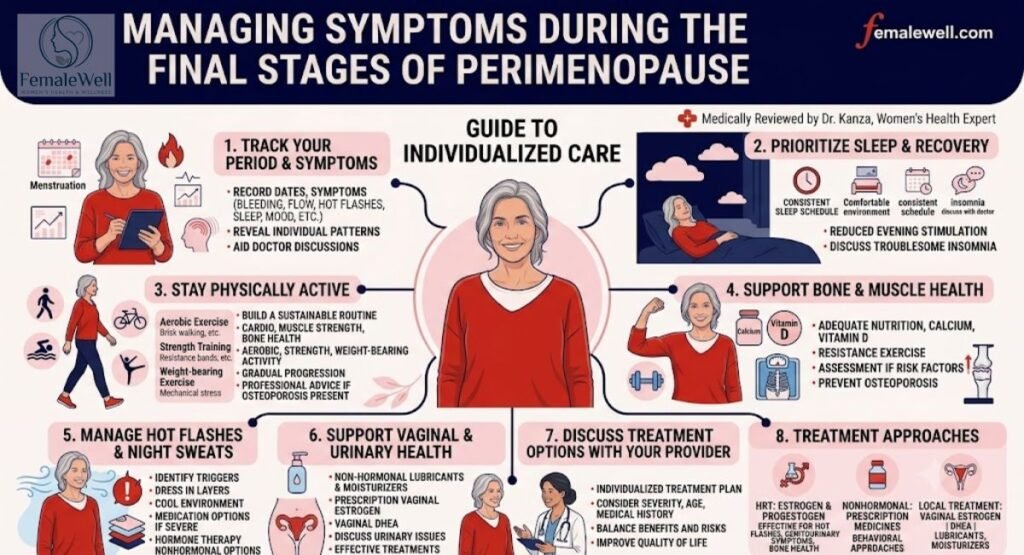
Actionable Strategy: Regular resistance strength training, weight-bearing exercise, and optimal Calcium/Vitamin D support bone health.
Tracking Your Late Perimenopause Timeline?
Remember that 12 consecutive months without a period is the gold-standard clinical diagnostic mark for full menopause.
Reviewed by Dr. Kanza
Additional Indicators
Other Symptoms You May Notice Near the End of Perimenopause
While period changes mark late perimenopause, shifting estrogen levels continue to affect various body systems. Here is what to monitor and when to consult your physician.
Breast tenderness can occur during periods of hormonal changes and fluctuating ovarian activity. Breast symptoms may change as cycles become irregular, although they are not among the most reliable signs perimenopause is ending.
Medical Note: Any new breast lump, persistent localized pain, skin change, or nipple discharge should be assessed separately rather than automatically attributed to menopause symptoms.
Changes in libido can occur during perimenopause and after menopause. Lower estrogen may contribute to vaginal dryness, reduced lubrication, and painful intercourse, while sleep problems, mood changes, medications, and relationship factors can also influence desire.
Action Plan: Vaginal health deserves proactive attention because localized treatments effectively relieve discomfort and protect long-term intimacy.
Brain fog can feel like forgetfulness, difficulty concentrating, or struggling to find familiar words. Hormonal changes, poor sleep, stress, and mood symptoms may all contribute.
The Menopause Society Insight: Cognitive changes during perimenopause are generally mild. Severe or persistent cognitive issues warrant a separate evaluation.
Headaches may change as ovarian hormone patterns shift. Women who experience hormonal migraines may notice increased symptoms during parts of perimenopause. Dizziness, however, has many potential causes.
Medical Note: Dizziness is not automatically a menopause symptom. New, severe, or persistent headaches and dizziness require assessment by a healthcare professional.
Declining estrogen affects skin hydration and collagen synthesis. You may notice drier skin, changes in skin texture, or hair thinning. The NHS includes dry, itchy skin and hair thinning among recognized transition symptoms.
Clinical Context: Because skin and hair shifts are not specific to late perimenopause, sudden or marked changes should be checked for thyroid or nutrient issues.
Fatigue can become frustrating during late perimenopause, especially when night sweats and mood symptoms disrupt sleep recovery.
Differential Diagnosis: Iron deficiency, thyroid dysfunction, sleep apnea, or mood disorders produce identical fatigue. Unexplained tiredness needs bloodwork verification.
Shifting temperature regulation causes daytime sweating, hot flushes, and night sweats. These vasomotor symptoms stem from alterations in the hypothalamus (the brain’s thermostat).
Duration Expectation: Symptom duration varies widely; while some women experience brief episodes, others continue having vasomotor shifts post-menopause.
Medical Reviewer Reminder (Dr. Kanza): Never assume new or severe symptoms are solely due to perimenopause. Always consult your healthcare provider to rule out underlying conditions.
How Do You Know Perimenopause Has Actually Ended?
There is an important difference between recognizing signs perimenopause is ending and knowing that menopause has actually occurred. Symptoms can suggest that you are approaching the end, but they cannot usually confirm the exact date of your final period. For someone who is not using hormonal contraception, natural menopause is generally identified retrospectively. The key is the absence of menstrual bleeding for 12 consecutive months. In other words, you normally know that menopause has occurred only after the final menstrual period has already passed.
The 12-Month Rule for Menopause
The commonly used definition of menopause is 12 months without a period when there is no other explanation and hormonal contraception is not masking menstrual bleeding. This is sometimes described as 365 days without a period. The important point is that the date is counted from the final menstrual period, not from the first missed period.
Once this milestone has been reached, you are considered to have entered postmenopause. The transition is therefore different from many medical conditions because the diagnosis often depends heavily on your menstrual history rather than one isolated blood test.
Clinical Guidance
What If Your Period Returns After Several Months?
A period returning after months of absence is common in late perimenopause, but distinguishing expected cycle variability from postmenopausal bleeding is vital for your health.
Cycle Restart vs. Menopause Confirmation
A period returning after several months without bleeding can happen during late perimenopause. It simply means that menopause has not yet been confirmed because the required 12-month period without menstruation has not been completed.
You may move between long gaps and unexpected periods during this final transition. However, unusual bleeding should not automatically be dismissed as purely hormonal. If bleeding is unusually heavy, prolonged, or occurs between periods, discuss it with a clinician.
Stage 1: Transition
Bleeding During Perimenopause
During perimenopause, menstrual bleeding can become heavier, lighter, longer, shorter, or more irregular. Occasional spotting can also occur as hormone production fluctuates unpredictable.
Key Rule: Distinguish between expected cycle variability and abnormal bleeding. Sudden changes, very heavy flows, or bleeding between periods require medical assessment by a GP.
Stage 2: Postmenopause
Bleeding After Menopause
Bleeding after menopause is fundamentally different. Once you have gone 12 consecutive months without a period, any subsequent vaginal bleeding must be evaluated.
Medical Priority: Postmenopausal bleeding can have benign causes, but it can also be an early indicator of cancer. Even light spotting or pink/brown discharge warrants evaluation.
Unsure About Your Bleeding Pattern?
Keep a daily symptom log of cycle gaps, spotting, or flow intensity to share directly with your healthcare professional.
Reviewed for Safety byDr. Kanza, Women’s Health Expert
Post-Transition Roadmap
What Happens After Perimenopause Ends?
Reaching menopause marks a major biological milestone. Understand how your hormonal baseline stabilizes, what happens to estrogen levels, and which symptoms evolve or persist into postmenopause.
Hormonal & Symptom Trajectory Across Stages
Click on any phase to explore clinical shifts and hormonal levels
→
→
→
HighFluctuatingLow Baseline
Rapid Fluctuation
Estrogen
Steep Decline
Estrogen
Low Constant
Estrogen
GSM Progression
GSM Risk
The Final Phase
Late Perimenopause
Characterized by long gaps between periods (60+ consecutive days). Ovarian hormone production fluctuates wildly, producing peak vasomotor symptoms like hot flushes and intense night sweats.
Estrogen StateUnpredictable Spikes & Drops
Dominant SymptomVasomotor & Mood Swings
The Diagnostic Point
Entering Menopause
Menopause is officially reached once you complete 12 consecutive months without a menstrual period. This single day marks the official boundary between perimenopause and postmenopause.
Estrogen StatePermanent Low Baseline
Clinical Criteria12 Months Amenorrhea
Postmenopausal Baseline
What Happens to Estrogen Levels & Symptoms?
Ovaries cease major estradiol production. While brain-related surges (hot flushes, night sweats, brain fog) gradually decrease in frequency over 2–5 years, lower hormonal levels create a new permanent baseline.
Systemic SymptomsGradual Reduction
Primary EstrogenEstrone (Conversion in fat)
Long-Term Health
How Vaginal and Urinary Symptoms Can Change
Unlike hot flashes, Genitourinary Syndrome of Menopause (GSM) does not resolve over time without intervention. Lower estrogen leads to thinning, drying, and loss of tissue elasticity in vaginal and bladder linings.
Tissue HealthProgressive Thinning / Dryness
Common RisksRecurrent UTIs, Urgency, Dyspareunia
12-Month Diagnostic Benchmark
Entering menopause is defined retrospectively after 12 full months without a period. Any bleeding after this mark warrants medical assessment.
Estrogen Level Plateau
Estrogen levels settle at a low, stable baseline rather than continually swinging up and down, which helps resolve hormone-driven mood swings.
Vaginal & Bladder Care
Vaginal dryness and urinary symptoms can persist or intensify post-menopause. Highly effective localized estrogen treatments and moisturizers are available.
Post-Menopause Wellness Roadmap
Long-Term Health Considerations After Menopause
The end of reproductive years creates a key opportunity to focus on long-term wellness. Lower estrogen and aging influence bone, cardiovascular, metabolic, and genitourinary health, but proactive care makes all the difference.
Key Health Focus Areas
Select or tap any slice to inspect specific clinical considerations
Bone Health25% Focus
Lower estrogen, aging, and lifestyle factors can influence several key physiological systems. These changes do not mean that illness is inevitable. Instead, this stage is an ideal time to review exercise, nutrition, blood pressure, cholesterol, glucose, smoking status, and personal risk factors.
Pillar 01
Bone Health
Bone density can decline around menopause, making osteoporosis and osteopenia important considerations. The body experiences a period of rapid bone loss around menopause followed by slower ongoing loss.
Key Strategy: Adequate calcium, vitamin D, resistance exercise, and weight-bearing activity support skeletal strength, alongside individualized clinical screening.
Pillar 02
Cardiovascular Health
Cardiovascular health deserves close attention because cardiovascular risk generally increases with age, and several key risk factors become more prominent post-menopause.
Key Strategy: Blood pressure, cholesterol, glucose, activity, diet, and non-smoking status all matter. A heart-healthy dietary pattern supports overall cardiovascular longevity.
Pillar 03
Metabolic Health
Changes in body composition and metabolism occur during midlife. Abdominal fat may become more prominent while muscle mass gradually declines with age.
Key Strategy: A balanced diet, adequate protein, regular exercise, and strength training support physical function. Metabolic health markers matter more than scale weight alone.
Pillar 04
Sexual and Genitourinary Health
Vaginal dryness, reduced lubrication, painful intercourse, and urinary symptoms can affect daily life, intimacy, and overall confidence throughout postmenopause.
Key Strategy: Local treatments such as vaginal estrogen, vaginal DHEA, and lubricants help relieve discomfort. Discuss options with a clinician who understands your history.
DK
Dr. KanzaWomen’s Health Expert
“Creating a personalized health plan with your healthcare professional helps identify which specific area deserves immediate attention for your unique body.”
Clinical Comparison Guide
Perimenopause vs. Menopause: What's the Difference?
The simplest distinction is that perimenopause describes the active transition toward the final menstrual period, while menopause is identified after 12 consecutive months without a period (when hormonal contraception is not obscuring the pattern). Postmenopause refers to all the years following menopause.
Feature
Perimenopause
Menopause
Postmenopause
Menstrual periods
Often irregular
No periods after the final menstrual period
No natural periods
Hormone pattern
Fluctuating
Ovarian hormone production has declined
Persistently lower ovarian estrogen
Hot flashes
Common
May occur
May continue
Sleep changes
Common
Common
May persist or improve
Vaginal symptoms
May begin
Can become noticeable
Can persist or increase
Pregnancy
Still possible
Natural conception is no longer expected after menopause is established
Natural conception is no longer expected
Diagnosis
Usually based on symptoms and menstrual history
Retrospective after 12 months without a period
Follows established menopause
Why Your Experience Is Unique
The transition is not identical for everyone. Some women experience substantial menopause symptoms, while others notice little beyond period changes. This natural biological variation is why comparing your individual timeline directly with another woman can create unnecessary worry.
Medical Evaluation Guide
When to See a Doctor About Perimenopause Symptoms
Many symptoms during midlife are normal variations of hormonal change. However, menopause should not become a catch-all explanation for every new symptom. Medical evaluation is vital when bleeding changes or when symptoms are severe or sudden.
Clinical Urgency vs. Lifestyle Impact Index
Comparing Medical Priority (Red) against Quality of Life Disruption (Navy)
Medical Priority / Urgency
Lifestyle & QoL Impact
Click or tap any bar cluster to inspect clinical evaluation guidelines
Urgent Priority
Heavy or Prolonged Menstrual Bleeding
Very heavy bleeding or prolonged flow deserves prompt medical attention rather than automatically being blamed on perimenopause. While hormonal fluctuations alter menstrual flow, fibroids, polyps, or other conditions can also cause abnormal bleeding.
Clinical Action: If bleeding is substantially heavier than your usual pattern, lasts unusually long, or causes weakness or dizziness, contact a clinician promptly.
High Priority
Bleeding Between Periods & Bleeding After Sex
Bleeding between periods or after intercourse should be assessed when new or persistent. While friction or delicate tissue contributes to postmenopausal spotting, infections, cervical changes, uterine polyps, or medications must be ruled out.
Clinical Action: Discuss new or repeated spotting between cycles or after sex with a GP to verify whether it fits expected transition patterns or requires further testing.
Critical Priority
Any Bleeding After Menopause
Any vaginal bleeding after established menopause requires formal evaluation. This includes light spotting, pink discharge, or brown discharge. While postmenopausal bleeding often stems from benign causes, it can sometimes be an early indicator of uterine cancer.
Clinical Action: Schedule a prompt appointment. Early clinical assessment significantly improves diagnostic precision and treatment outcomes.
Urgent Evaluation
Severe Pelvic Pain or New Sudden Symptoms
Severe pelvic pain is not a defining sign that perimenopause is ending. New, intense pain can stem from gynecological, urinary, or gastrointestinal issues. Similarly, sudden neurological symptoms, severe headaches, or unexplained weight loss deserve proper diagnosis.
Clinical Action: Do not place sudden or severe pain under the broad label of "normal menopause." Seek immediate medical investigation.
Quality of Life
Symptoms That Interfere With Daily Life
You do not need to simply tolerate debilitating symptoms because they are related to midlife changes. Severe hot flashes, insomnia, anxiety, or vaginal discomfort can impact work, relationships, and wellbeing.
Clinical Action: Speak with a healthcare professional about evidence-based management, HRT, lifestyle adjustments, and non-hormonal treatment options.
What Happens During Your Medical Evaluation?
A healthcare professional will review your menstrual history, medications, contraception, and personal risk factors. Depending on your situation, they may recommend physical examination, pelvic ultrasound, or blood tests. Routine hormone testing is not usually needed for typical menopause after age 45, but can be appropriate in selected circumstances.
Clinical StandardsDr. Kanza Sarfraz, Medical Reviewer
Frequently Asked Questions
Common Questions About the End of Perimenopause
The end of perimenopause can feel uncertain because symptoms rarely follow a predictable sequence. Below are clinical answers to common concerns regarding late-stage perimenopause, menstrual changes, and the postmenopause transition.
The strongest clues include increasingly irregular periods, longer gaps between periods, and eventually the complete absence of menstruation. Other signs perimenopause is ending may include changing hot flashes, sleep patterns, mood symptoms, or headaches. None of these symptoms alone confirms menopause—menopause is generally recognized retrospectively after 12 consecutive months without a period.
Yes. During late perimenopause, menstrual cycles often become increasingly unpredictable. Some women may go several weeks or months without bleeding before another period occurs. The Menopause Society notes that skipped intervals of 60 days or more can occur during the late transition, although the pattern varies considerably between individuals.
Yes. Symptoms can improve or disappear temporarily and later return. Hormone fluctuations are not perfectly predictable, so a symptom-free period does not necessarily mean that menopause has already occurred. Some symptoms also improve while others become more noticeable. This is why symptom duration alone cannot establish the end of perimenopause.
They can. Some women experience increasingly bothersome hot flashes during the menopause transition, while others have milder or intermittent symptoms. Eventually, many women experience improvement, but the timing varies. Night sweats and other vasomotor symptoms can also continue after menopause, so their presence does not necessarily mean that perimenopause is still underway.
Yes. Menstrual changes are common, but symptoms can appear before periods become dramatically irregular. You may experience hot flashes, mood changes, sleep problems, or headaches while still having relatively regular menstrual cycles. The menopause transition develops gradually, so symptoms and period changes do not always occur simultaneously.
There is no fixed duration for the final stage of perimenopause. Some women progress relatively quickly, while others experience irregular cycles and symptoms for years. Current NHS guidance notes that menopause and perimenopause symptoms can last several years and sometimes longer.
Yes. Pregnancy remains possible during perimenopause because ovulation can still occur even when periods become irregular. If you do not want pregnancy, continue using appropriate contraception until menopause has been confirmed according to medical guidance for your age and contraceptive method.
If you are not using hormonal contraception and there is no other clinical explanation, 12 consecutive months without a period marks menopause. You then officially enter postmenopause. The exact date of menopause is identified retrospectively because you cannot know a period was your final one until the required 12-month interval has passed.
Yes. Some postmenopausal symptoms can continue after the final menstrual period. Hot flashes, sleep problems, joint symptoms, vaginal dryness, and urinary symptoms may persist. Genitourinary symptoms can become more noticeable over time without treatment, so persistent vaginal or urinary problems deserve appropriate medical support.
No. Bleeding after menopause should always be checked by a healthcare professional, even when it happens only once or appears as light spotting. While postmenopausal bleeding is often caused by non-cancerous conditions, it can sometimes be a sign of cancer. Prompt medical assessment is essential.
No matching questions found. Try searching for terms like "bleeding", "hot flashes", or "pregnancy".
Executive Summary
Key Takeaways: Recognizing the End of Perimenopause
The signs that perimenopause is ending usually appear as a gradual pattern rather than a single dramatic event. Understanding what to track and when to seek medical support can help you navigate this final stage with confidence.
01
Pattern of Cycle Changes
Periods become increasingly irregular, gaps grow longer, and menstruation eventually ceases. While hot flashes, mood shifts, migraines, and sleep disturbances may evolve, symptoms alone cannot confirm menopause without menstrual tracking.
02
The 12-Month Milestone
The definitive clinical milestone is 12 consecutive months without a period (when not obscured by hormonal contraception). Reaching this threshold marks the official entry into postmenopause.
03
Postmenopausal Symptoms
While vasomotor symptoms like hot flashes may improve over time, other changes—particularly genitourinary, vaginal, and urinary symptoms—can persist or become more noticeable without ongoing care.
04
Proactive Self-Care & Health
Track your symptoms, safeguard bone density, stay physically active, and do not simply "wait it out." Evidence-based symptom management and tailored treatments exist to protect your long-term quality of life.
When Professional Assessment Is Essential
Heavy bleeding, bleeding between periods, or any vaginal bleeding after postmenopause is established requires prompt evaluation by a clinician.
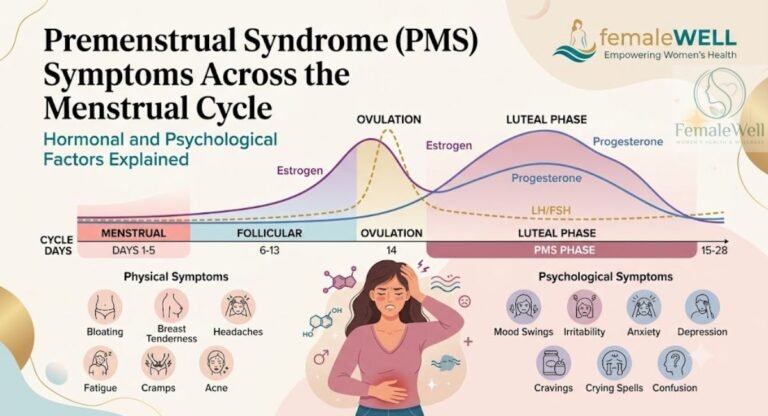
Premenstrual Syndrome (PMS) Symptoms Across the Menstrual Cycle: Hormonal and Psychological Factors Explained
Understand how estrogen, progesterone, and neurotransmitters drive physical and emotional changes throughout your monthly cycle—backed by medical expert insight.
Medically Reviewed byDr. KanzaWomen’s Health Expert
7 Min Read
Updated:
Key Takeaways In This Guide:
Cycle Dynamics: How hormone fluctuations shift across Follicular, Ovulatory, and Luteal phases.
Physical vs. Emotional: Identifying root causes behind bloating, cramps, anxiety, and mood swings.
Science-Backed Relief: Doctor-approved strategies to stabilize mood and balance cycle symptoms.
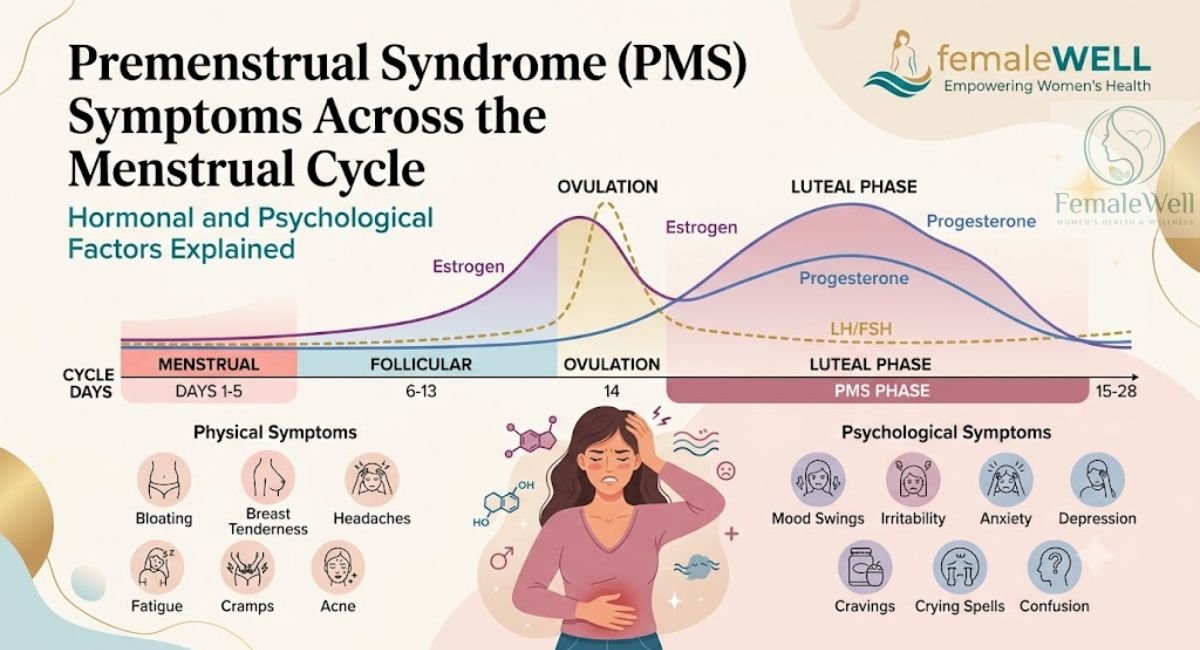
For many women, the days before menstruation can bring a noticeable shift in how the body and mind feel. Premenstrual Syndrome (PMS) symptoms may include breast tenderness, bloating, headaches, fatigue, food cravings, irritability, anxiety and changes in mood. These symptoms often follow a recurring pattern during the menstrual cycle, particularly during the luteal phase after ovulation. However, PMS is not simply a matter of having “too many” or “too few” hormones. Research suggests that some people may be more sensitive to normal fluctuations in estrogen, progesterone and related neuroactive compounds.
At the same time, psychological factors, stress, sleep quality and emotional wellbeing can influence how symptoms are experienced. Understanding these interactions can help you recognize your personal pattern and distinguish typical PMS from more severe conditions such as PMDD. This guide explores the hormonal and psychological factors behind PMS symptoms across the menstrual cycle.
What Is Premenstrual Syndrome (PMS)?
PMS describes a recurring collection of physical, emotional and behavioral symptoms that appear in relation to the menstrual cycle. Common experiences include mood changes, irritability, anxiety, tiredness, headaches, bloating, breast tenderness, appetite changes and sleep problems. Importantly, symptoms vary between people and can change from one cycle to another. What makes PMS different from an occasional difficult day is its cyclical pattern. Symptoms tend to emerge during the premenstrual phase and improve around or after menstrual onset. This timing matters because headaches, low mood or fatigue that remain present throughout the month may have another explanation. A symptom diary can therefore reveal more than a single blood test ever could.
When Do PMS Symptoms Usually Begin?
The days leading up to menstruation are the period most commonly associated with PMS. NHS guidance notes that symptoms can start or intensify during the two weeks before a period and usually ease after menstruation begins. The exact timing varies because ovulation and cycle length differ between individuals.
How PMS Differs From Normal Menstrual Changes
Normal menstrual cycle phases involve substantial biological changes. Those changes do not automatically represent a disorder. PMS becomes more relevant when recurring symptoms cause noticeable distress or interfere with daily functioning. In other words, feeling slightly tired before your period is not the same clinical situation as repeatedly being unable to work because of severe mood or physical symptoms.
Clinical Comparison
PMS vs. Premenstrual Dysphoric Disorder (PMDD)
PMS and premenstrual dysphoric disorder exist on a related spectrum but are not interchangeable terms. PMDD involves more severe symptoms, particularly mood-related symptoms such as marked irritability, anxiety, or depressed mood. The symptoms can significantly affect relationships, work, and social functioning. NHS guidance also emphasizes the importance of seeking help when PMDD symptoms become severe.
Key Differences Between PMS and PMDD
Summary of clinical indicators and impact
Feature
PMS
PMDD
Physical symptoms
Common
Common
Emotional symptoms
Possible
Often prominent
Symptom severity
Variable
Often severe
Daily functioning
May be affected
Frequently affected
Cyclical timing
Important
Essential
Clinical assessment
Symptom history and pattern
Prospective symptom assessment is particularly important
Note: On mobile devices, swipe horizontally to view all table columns.
Understanding the Clinical Threshold
The dividing line is not simply whether someone feels miserable before menstruation. Clinicians consider the number and type of symptoms, their symptom timing, severity, and impact on everyday life. PMDD diagnostic criteria place particular emphasis on recurring affective symptoms and functional impairment.
How PMS Symptoms Change Throughout the Menstrual Cycle
Think of the menstrual cycle phases as a moving biological landscape rather than four rigid boxes. Estrogen, progesterone and other reproductive signals rise and fall in sequence. Meanwhile, your brain, metabolism, sleep, appetite and emotional systems respond to those changes. This is why symptoms across the menstrual cycle can look completely different from one phase to another.
For someone with PMS, the most noticeable changes often occur after ovulation and during the late luteal phase. Yet symptoms do not always wait until the final few days. Some people notice early luteal changes while others experience a sharper shift closer to menstrual onset. Research therefore focuses heavily on menstrual cycle timing rather than assuming every person follows the same calendar.
The Main Phases of the Menstrual Cycle
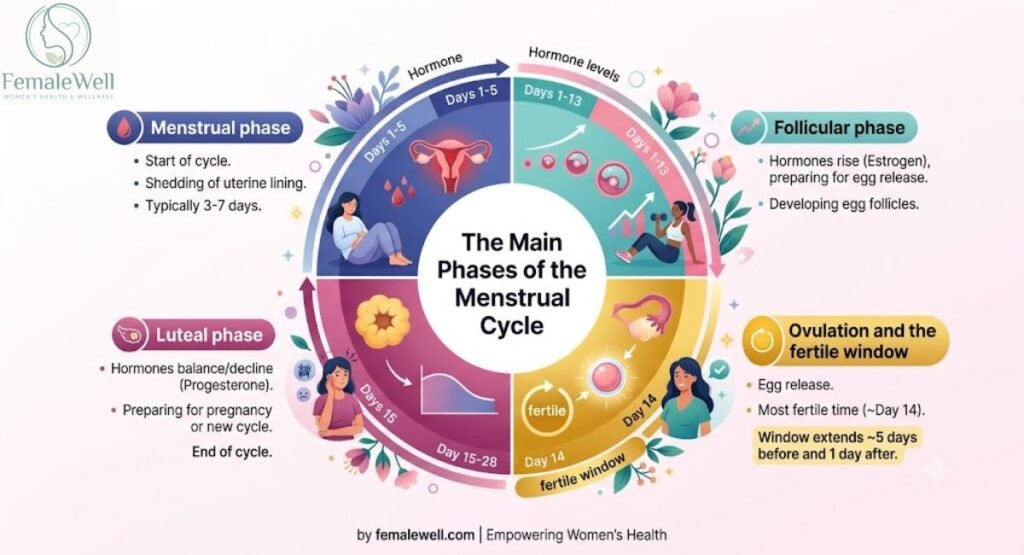
The classic cycle includes menstruation, the follicular phase, ovulation and the luteal phase. Each stage has its own hormonal environment. Understanding those transitions makes it easier to see why late-cycle symptoms can emerge after a relatively symptom-free period earlier in the cycle.
Menstrual phase
The menstrual phase begins on the first day of menstrual bleeding. Ovarian hormone levels have fallen after the previous cycle failed to result in pregnancy. Cramps, fatigue, headaches and other menstrual symptoms may occur here, but symptoms caused by menstruation should not automatically be labeled PMS.
Follicular phase
During the follicular phase, ovarian follicles develop and estradiol generally rises as the body prepares for ovulation. Many people report fewer premenstrual symptoms during this part of the cycle. However, individual experiences vary, and the absence of PMS-type symptoms does not mean that every person feels physically or emotionally identical during the follicular phase.
Ovulation and the fertile window
Ovulation marks a major turning point in the ovulatory cycle. A rise in luteinizing hormone, commonly called the LH surge, triggers ovulation. The fertile window surrounds this event because sperm can survive for several days while the egg remains viable for a shorter period. Some people also notice mild mid-cycle abdominal pain, known as mittelschmerz.
Luteal phase
After ovulation, the corpus luteum produces progesterone. This creates the hormonal environment of the luteal phase. Progesterone rises and later falls if pregnancy does not occur. For people who experience PMS, this post-ovulatory period is especially important because symptoms can emerge during the luteal phase and become stronger as menstruation approaches.
Hormonal Timeline
When PMS Symptoms Typically Emerge
The exact PMS symptom emergence point differs from person to person. Some individuals notice changes soon after ovulation, while others remain comfortable until the final days of the cycle. Research describes early, middle, and late luteal patterns rather than one universal starting day.
Why Symptoms Increase Before Menstruation
The days before menstrual onset involve a changing endocrine environment. Progesterone and its neuroactive metabolites decline after reaching their luteal peak, alongside changes in estradiol.
In susceptible individuals, these transitions influence brain pathways involved in mood, sleep, appetite, and emotional regulation—even when hormone concentrations are clinically normal.
What Happens When Menstruation Begins?
For many people, PMS symptoms decrease noticeably once menstruation begins. NHS guidance describes symptoms as generally easing after the period starts.
Key Clinical Indicator: This symptom-free interval helps distinguish a true cycle-linked pattern from symptoms persisting continuously.
Data Insight & Neuro-Sensitivity
Hormonal Factors & PMS Symptom Dynamics
Comparative analysis showing how central nervous system sensitivity amplifies premenstrual symptoms compared to absolute blood hormone levels.
Neuro-Hormonal Impact Scale
Absolute Level Impact CNS Sensitivity Impact
Estrogen & PMSSerotonin & Vascular Impact
45%
85%
Progesterone & PMSGABA Receptor Reaction
40%
90%
Estrogen / Progesterone RatioLuteal Shift Speed
50%
80%
Cortisol & Stress ResponseHPA Axis Amplification
60%
75%
Are Symptoms Caused by High or Low Levels?
No. Research confirms that individuals with severe PMS rarely have abnormally high or low concentrations of estrogen or progesterone. Their endocrine serum levels mirror those without PMS symptoms.
Why Hormone Sensitivity Matters More
It is the brain’s unique molecular sensitivity to normal hormonal declines (particularly allopregnanolone drops) that triggers serotonin dysregulation, mood changes, anxiety, and fluid retention.
Psychological Factors That May Influence PMS
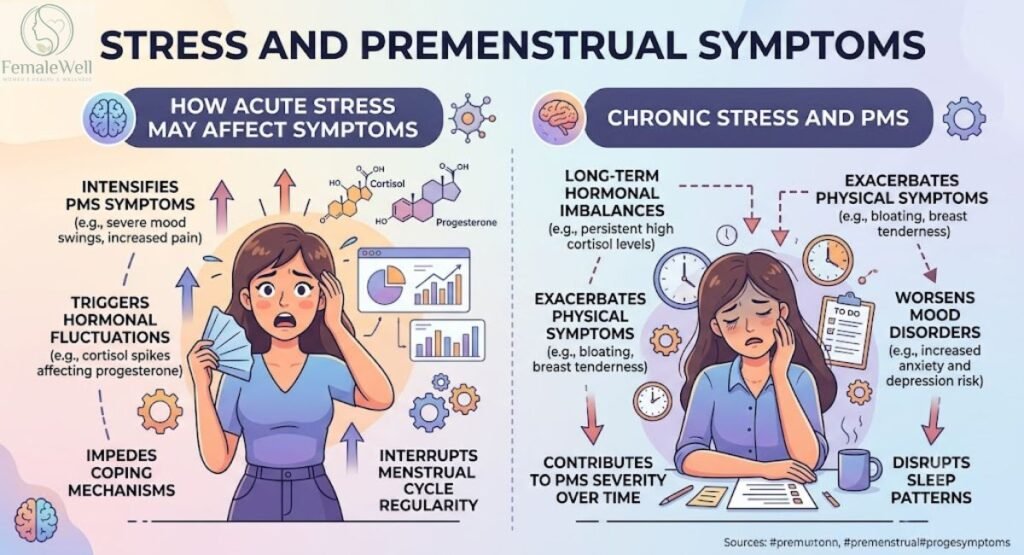
PMS is not imaginary and it is not simply a problem of attitude. At the same time, psychological factors can influence how symptoms develop and how strongly they are experienced. Stress, sleep quality, anxiety, emotional regulation and social pressures can interact with biological changes. The result is a genuine brain-body experience that cannot be neatly separated into “physical” and “psychological” boxes.
The modern view is therefore biopsychosocial. Psychological predictors of PMS do not replace hormonal explanations. Instead, they may modify symptom expression. Someone facing chronic work pressure, poor sleep and relationship conflict may experience a different premenstrual month from the same person during a calm period. Research increasingly examines these individual differences rather than searching for one universal PMS mechanism.
Mood & Psychological Axis
Psychological Factors & PMS
How brain neurochemistry, personality traits, sleep, and stress shape premenstrual emotional and physical health.
01
Anxiety & Mood Changes
Luteal drops in progesterone and serotonin alter brain circuit reactivity, triggering sudden anxiety, mood swings, and emotional sensitivity before menses.
02
Neuroticism & Sensitivity
Individual traits like higher stress sensitivity or neuroticism lower emotional resilience, making normal premenstrual shifts feel noticeably more severe.
03
Sleep & Emotional Health
Progesterone shifts disrupt REM and deep sleep during the luteal phase. Poor sleep directly worsens emotional instability and daytime irritability.
04
Stress & Physical Link
Psychological stress amplifies central pain pathways—turning internal stress directly into heightened cramps, tension headaches, and fatigue.
Common PMS Symptoms and When They Appear
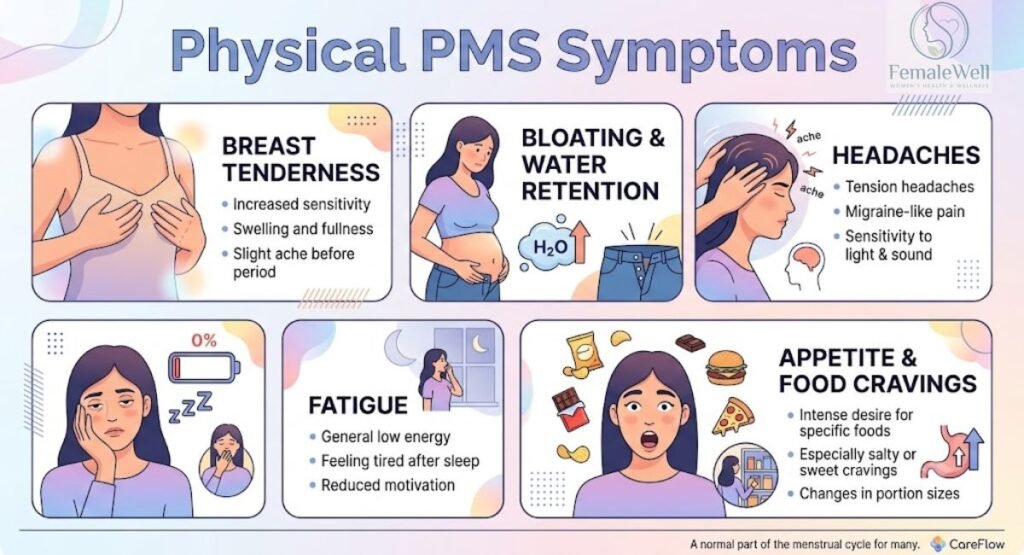
PMS can feel like a collection of unrelated problems until you place them on a timeline. Breast tenderness may appear alongside bloating. Fatigue may arrive with irritability. Food cravings may accompany poor sleep. These combinations are not unusual. NHS guidance lists mood changes, anxiety, tiredness, bloating, breast tenderness, headaches and appetite changes among common PMS experiences.
The important clue is not whether you recognize one symptom. It is whether several cyclical symptoms repeatedly follow a similar pattern. Your symptom profile may also change over time. One month may bring headaches and breast tenderness while another produces more emotional symptoms. That cycle-to-cycle variability does not automatically mean the pattern is unrelated to menstruation.
Clinical Cyclicity
Emotional and Psychological Symptoms
PMS mood shifts affect relationships and self-perception. Their key indicator is cyclicity: appearing premenstrually and receding after menses.
Cyclic Shift
Irritability & Mood Swings
A shorter fuse where small frustrations feel overwhelming. Tracking helps distinguish recurring luteal conflict from general stress.
PMDD Relevant
Anxiety & Worry
Premenstrual restlessness or feeling unable to cope. If anxiety persists all month, assess for a general anxiety disorder.
Affective Shift
Low Mood & Feeling Flat
Temporary emotional flatness. Diagnostic certainty depends on confirming a clear, symptom-free period post-menstruation.
Cognitive
Concentration & Brain Fog
Focus difficulties driven by poor luteal sleep and fatigue. Record alongside sleep and mood rather than as an isolated effect.
How to Track PMS Symptoms and Identify Your Personal Pattern
If you want to understand your own PMS pattern, start with observation rather than guesswork. PMS symptom tracking can show whether symptoms reliably appear during the same portion of the cycle. It can also reveal something equally important: perhaps a symptom you blamed on PMS actually persists throughout the month.
A simple daily record can become valuable clinical evidence. NHS guidance recommends keeping a symptom diary for at least two menstrual cycles when assessing PMS or PMDD. The goal is not to become obsessed with every sensation. Instead, you are creating a timeline that makes otherwise invisible cyclical changes easier to recognize.
Diagnostic Protocol
What to Track During Each Menstrual Cycle
Key parameters to log consistently for establishing clinical cyclicity and identifying PMS/PMDD patterns.
Physical SymptomsBloating, cramps, breast tenderness, headaches
Clinical Tip: Log daily for at least 2–3 consecutive cycles to clearly isolate luteal phase symptom patterns.
When PMS Symptoms May Require Medical Evaluation
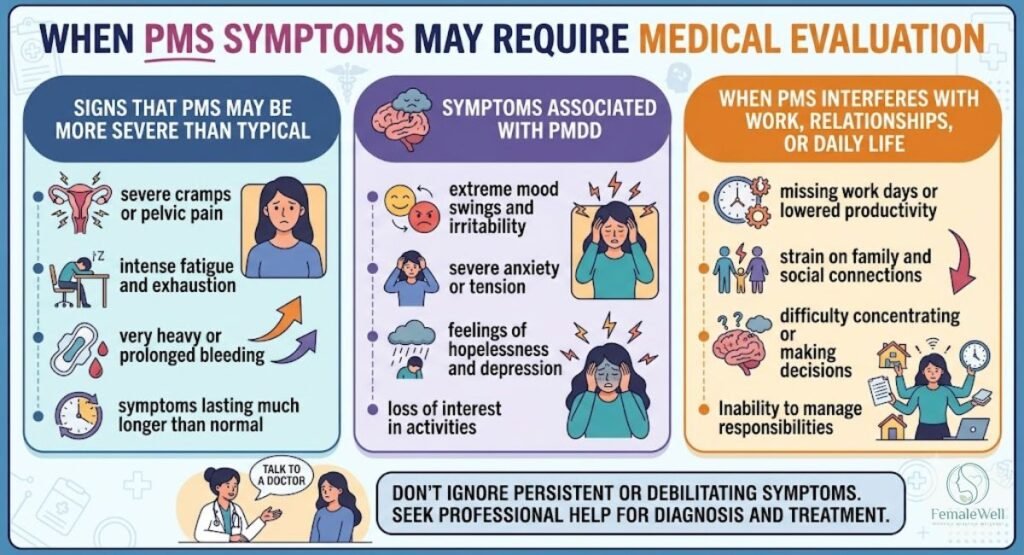
PMS deserves medical attention when it repeatedly interferes with your life. You should not have to accept severe symptoms as something you simply need to endure because they happen every month. Clinical PMS can affect work, relationships and wellbeing, while PMDD can produce substantial emotional impairment. Effective assessment begins by understanding the pattern rather than dismissing the symptoms.
Medical evaluation becomes particularly important when symptoms are severe, new, progressively worsening or present outside the expected premenstrual window. Persistent fatigue, depression, anxiety, pain or abnormal bleeding may have causes unrelated to PMS. A clinician can consider the menstrual pattern alongside your broader reproductive and general health.
What a Healthcare Professional May Evaluate
Assessment usually begins with your symptom history and menstrual pattern. A clinician may also consider medications, contraception, mental health, sleep, stress, and other medical conditions. Prospective symptom records can make this conversation much more productive because they show menstrual timing rather than relying entirely on memory.
Prospective Symptom Severity Across a 28-Day Cycle
A visual representation of how symptom tracking pinpoints PMS/PMDD timing relative to menstruation.
SevereModerateMildNone
Follicular Phase (Days 1–13)
Ovulation (Day 14)
Luteal Phase / PMS Window (Days 15–28)
Note: Notice how severe symptoms peak sharply during the luteal phase and resolve abruptly with the onset of menstruation (Day 1).
🩸
Menstrual and Symptom History
Your clinician may ask when symptoms start, how long they last, and whether they disappear after menstruation. They may also ask about cycle length, bleeding, and the number of symptom-free days. A prospective diary can help establish whether your symptoms meet a recognizable pattern of clinical-level symptoms.
🧠
Mental Health and Stress Factors
A clinician may ask about anxiety, depression, sleep, work pressure, and relationship stress. This does not mean your symptoms are being dismissed as psychological. Instead, these questions help identify psychosocial factors that may intensify symptoms or reveal a condition that deserves separate treatment.
🔍
Possible Underlying Conditions
Symptoms that resemble PMS can occur with other conditions. Depending on your history, a clinician may consider thyroid disorders, migraine, anemia, endometriosis, adenomyosis, depression, anxiety disorders, or perimenopause. The aim is not to find another diagnosis at all costs. It is to avoid assuming that every recurring symptom is automatically PMS.
Questions to Ask Your Doctor About Persistent Premenstrual Symptoms
A useful medical conversation can begin with simple questions. Bringing several months of records can make these questions far easier to answer:
Is my symptom pattern consistent with standard PMS or PMDD?
Would prospective tracking for 2–3 months provide clearer diagnostic insight?
Could another underlying medical condition explain or exacerbate my symptoms?
How might my current medications or contraception options influence this pattern?
FAQs About PMS and Hormones
Understanding PMS becomes easier when the most common questions have straightforward answers. The central theme remains the same: symptom timing matters. Hormonal fluctuations provide the biological backdrop, but individual sensitivity and psychological context help shape what you actually experience.
There is no universal PMS day because menstrual cycles and ovulation timing differ. Symptoms commonly develop during the luteal phase and may become stronger during the days before menstrual onset. NHS guidance notes that PMS symptoms can occur during the two weeks before a period. Tracking your own cycle is more informative than relying on one fixed calendar day.
No single hormone explains every case. Hormones and PMS are connected through changes in estrogen, progesterone and neuroactive steroid pathways. Current research increasingly emphasizes sensitivity to hormonal fluctuations rather than simply having an abnormally high or low hormone concentration.
Stress can interact with PMS symptoms, although the relationship is not a simple cause-and-effect equation. Higher momentary stress levels, poor sleep and emotional strain can affect pain, mood and coping. Research into PMDD also suggests that altered luteal-phase stress sensitivity may involve interactions between neuroactive steroids and the HPA axis.
Yes. Symptoms can appear during the early luteal phase after ovulation, although many people notice stronger symptoms later. Research has reported early, middle and late luteal symptom emergence. Therefore, symptoms after ovulation can still fit a premenstrual pattern when they consistently resolve around menstruation.
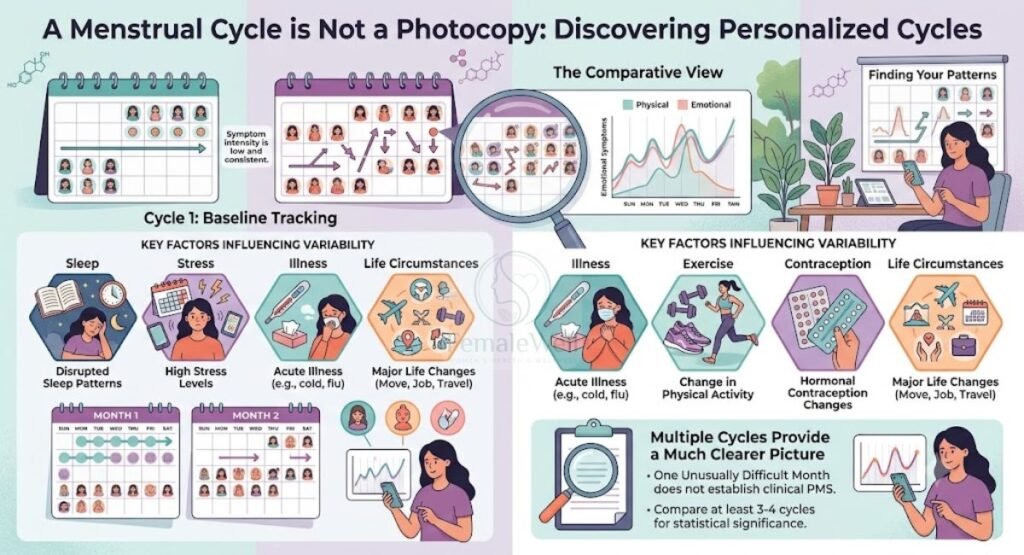
Your body does not repeat every cycle under identical conditions. Daily stressors, sleep, illness, lifestyle, hormonal contraception and cycle timing can all influence symptom experience. Biological sensitivity may also vary. Tracking multiple cycles can reveal whether differences represent ordinary variation or a meaningful change in your usual pattern.
Yes. Having normal hormone levels does not rule out PMS. The problem may involve how the brain responds to ordinary hormone fluctuations and mood rather than an endocrine abnormality. Research on PMDD particularly emphasizes altered sensitivity to neuroactive steroids and their effects on GABA-related brain pathways.
PMS can involve physical and emotional symptoms that vary in severity. PMS and PMDD differ mainly in severity, symptom profile and functional impact. PMDD is characterized by prominent and clinically significant mood symptoms that recur in relation to the menstrual cycle. If symptoms substantially affect your life, professional assessment is appropriate.
The strongest practical clue is repetition. Record symptoms every day across at least two cycles and compare them with ovulation and menstrual timing where possible. If symptoms repeatedly appear during the same premenstrual period and then improve after menstruation, that provides evidence of a cyclical relationship. NHS guidance recommends symptom diaries as part of PMDD assessment.
Women’s Health & Hormones
Medically Reviewed
12 Min Read
30 Natural Ways to Help Manage PCOS: Diet, Supplements, Lifestyle & More
Polycystic Ovary Syndrome doesn’t have to control your daily life. Discover evidence-based, clinical-backed natural remedies to balance hormones, stabilize insulin levels, reduce inflammation, and regain your energy.
Join 45,000+ women managing PCOS. Unsubscribe anytime.
30Proven Tips
100%Doctor Backed
FreePDF Guide
Success!Action completed.
Polycystic ovary syndrome, or Polycystic ovary syndrome, can affect your menstrual cycle, metabolism, skin, hair growth and reproductive health. If you have been searching for natural remedies for PCOS, you have probably seen hundreds of promises online. Some are sensible. Others are far less convincing.
The good news is that meaningful PCOS lifestyle changes do not need to involve extreme diets or miracle supplements. Nutrition, regular exercise, sleep, stress management and appropriate medical care can all play useful roles. However, PCOS is a complex condition, so there is no single natural PCOS treatment that works for everyone. The 2023 international guideline emphasizes sustainable lifestyle habits and individualized care rather than one universal diet or exercise prescription.
Important: Natural approaches can support PCOS treatment, but they should not replace appropriate medical evaluation or prescribed treatment. This is especially important when you have persistent irregular periods, fertility concerns, heavy bleeding or significant metabolic risk factors.
1. Start With a PCOS-Friendly Diet
Food is one of the easiest places to begin making practical changes. A balanced PCOS diet does not mean you must eliminate entire food groups. Instead, focus on nutritious PCOS-friendly foods, adequate protein, fiber-rich carbohydrates and unsaturated fats. A Mediterranean-style pattern can be useful because it naturally emphasizes vegetables, legumes, whole grains, fish, olive oil, nuts and minimally processed foods. The broader goal is a sustainable eating pattern that supports metabolic and overall health rather than a rigid diet.
A useful meal can be surprisingly simple. You might combine lentils with vegetables and whole grains or pair fatty fish with roasted vegetables and potatoes. These choices provide different nutrients while making meals satisfying. There is also no strong evidence that every person with PCOS needs a low-carb diet or low-calorie diet. Your eating pattern should reflect your preferences, culture, nutritional needs and health goals.
Evidence-Based Nutrition
8 PCOS-Friendly Diet Strategies for Hormonal Balance
A balanced diet can help manage PCOS symptoms by improving insulin sensitivity, reducing inflammation, and stabilizing energy levels.
01Insulin Focus
Choose More Whole Foods
Unprocessed, whole foods provide intact nutrients and fiber that slow digestion, prevent insulin spikes, and promote sustained satiety.
Insulin Impact Score95%
Best Sources: Quinoa, wild berries, raw nuts, fresh greens, oats.
02Insulin Focus
Balance Your Meals
Pairing complex carbohydrates with lean protein and healthy fats prevents rapid glucose absorption, keeping blood sugar stable throughout the day.
Glucose Stability90%
Macro Formula: ½ Vegetables + ¼ Lean Protein + ¼ Fiber-Carbs + Healthy Fat.
03Insulin Focus
Increase Dietary Fiber
Fiber binds to excess hormones in the digestive tract, promotes a healthy gut microbiome, and improves long-term insulin sensitivity.
Gut & Hormone Benefit88%
Best Sources: Chia seeds, flaxseeds, lentils, avocado, broccoli.
04Anti-Inflammatory
Include Anti-Inflammatory Foods
Chronic low-grade inflammation drives excess androgen production. Omega-3s and antioxidants soothe cellular stress and support ovarian health.
Inflammation Reduction92%
Best Sources: Wild salmon, extra virgin olive oil, turmeric, blueberries.
05Hormone & Mineral
Pay Attention to Iron
PCOS can involve heavy menstrual bleeding or absent periods (amenorrhea). Tailor iron intake based on lab tests and period blood flow.
Energy & Oxygen Support80%
Best Sources: Spinach, grass-fed beef, pumpkin seeds + Vitamin C.
06Hormone & Mineral
Include Magnesium-Rich Foods
Magnesium improves insulin sensitivity, calms the nervous system, decreases menstrual cramps, and supports restorative sleep quality.
Stress & Sleep Support86%
Best Sources: Dark chocolate (>70%), almonds, pumpkin seeds, leafy greens.
07Insulin Focus
Reduce Refined Sugars
Ultra-processed sugars create rapid glucose spikes, worsening insulin resistance and triggering increased androgen production in ovaries.
Hormone Defense94%
Healthy Swap: Swap sugary drinks for fruit-infused water or herbal teas.
08Hormone & Mineral
Understand Caffeine Response
High caffeine can increase cortisol (stress hormone) levels and disrupt sleep. Observe how your body responds to find your optimal threshold.
Adrenal Balance75%
Gentle Swaps: Matcha green tea, golden milk latte, spearmint tea.
Focus on Whole, Minimally Processed Foods
Strategy #1: Choose more whole foods: Build your meals around vegetables, fruit, legumes, nuts, seeds, whole grains and other minimally processed foods. Whole foods provide fiber, vitamins, minerals and other compounds that support general metabolic health. Leafy greens, broccoli, berries, lentils and beans can all fit naturally into a balanced PCOS diet without requiring complicated recipes or expensive specialty products.
Balance Carbohydrates With Protein and Healthy Fats
Strategy #2: Balance your meals: Instead of fearing carbohydrates, combine them with protein and healthy fats. For example, you might eat oats with yogurt and nuts or whole-grain toast with eggs and avocado. This approach can make meals more satisfying and may help you avoid the rapid hunger that sometimes follows highly refined meals. It is more flexible than automatically adopting a restrictive diet.
Choose High-Fiber Foods
Strategy #3: Increase dietary fiber: Beans, lentils, vegetables, fruit, seeds and whole grains can increase fiber intake while adding texture and variety. Foods such as spinach, berries, Brussels sprouts, chickpeas and oats can be especially useful choices. Fiber also supports digestive health and can contribute to fullness, which may make long-term weight management easier without relying on extreme restriction.
Why Fiber May Help With Blood Sugar Control
Fiber can influence how quickly food is digested and absorbed, particularly when it replaces highly refined carbohydrates. This matters because blood sugar, insulin sensitivity and insulin resistance are relevant metabolic considerations in PCOS. However, fiber is not a standalone cure for PCOS. Think of it as one useful piece of a broader eating pattern that supports insulin metabolism and overall metabolic health.
Include Anti-Inflammatory Foods
Strategy #4: Include more anti-inflammatory foods: Vegetables, fruit, legumes, nuts, seeds, fish and olive oil can form the foundation of an eating pattern rich in beneficial nutrients. Some people use the term “anti-inflammatory diet” as though it were a specific medical treatment. It is better understood as a general dietary pattern that may support overall health rather than a guaranteed way to correct inflammation or oxidative stress associated with PCOS.
Add Iron-Rich Foods When Needed
Strategy #5: Pay attention to iron when appropriate: Iron-rich foods include meat, seafood, beans, lentils, fortified grains and leafy greens. This nutrient deserves particular attention if you experience heavy menstrual bleeding because ongoing blood loss can contribute to deficiency. However, do not automatically start an iron supplement based on symptoms alone. A clinician can assess your history and laboratory results before recommending supplementation.
Get Enough Magnesium From Food
Strategy #6: Include magnesium-rich foods: Nuts, seeds, legumes, whole grains and leafy greens can provide magnesium as part of a balanced diet. Almonds, cashews, pumpkin seeds and beans are practical options. Magnesium has important roles throughout the body, but eating magnesium-rich foods should not be confused with evidence that high-dose magnesium supplements specifically treat PCOS. Food first is usually a sensible starting point.
Limit Added Sugar and Highly Refined Carbohydrates
Strategy #7: Reduce frequent intake of added sugars and highly refined foods: Sugary drinks, sweets and heavily refined snacks can make it harder to maintain a nutrient-dense eating pattern. You do not need to ban every dessert. Instead, consider frequency, portion size and what you eat most often. Replacing some refined foods with whole grains, legumes, vegetables and fruit can support a more balanced approach to blood sugar management.
Consider Your Caffeine Intake
Strategy #8: Understand your response to caffeine:Coffee and green tea can fit into many healthy eating patterns, but caffeine can affect sleep, anxiety, heart rate and individual well-being. There is not strong evidence that every person with PCOS needs to eliminate caffeine. Instead, consider how much you consume and whether it contributes to sleep disturbances, stress or other symptoms.
Does Coffee Affect PCOS Symptoms?
Claims that coffee automatically worsens PCOS are stronger than the evidence supports. Your response may depend on quantity, timing and individual tolerance. If coffee makes you restless or interferes with sleep hygiene, reducing it may be worthwhile. If you tolerate moderate caffeine well, there is no established rule requiring universal coffee avoidance simply because you have PCOS.
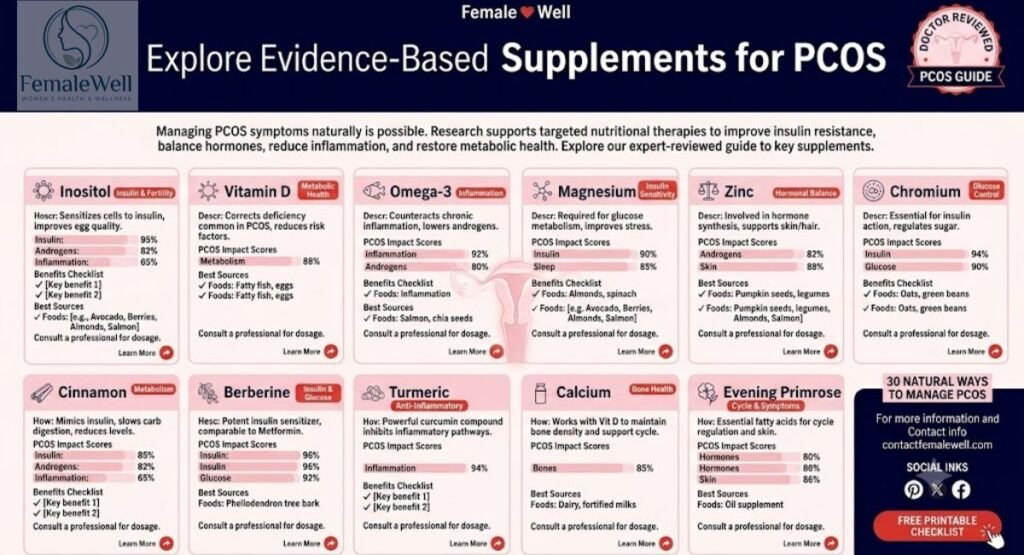
2. Explore Evidence-Based Supplements for PCOS
Supplements receive enormous attention in the PCOS world, but popularity is not the same as proof. Dietary supplements can contain vitamins, minerals, botanicals or other ingredients, and the evidence varies substantially between products. Research findings can also differ because studies use different formulations, doses and populations. For that reason, supplements should be viewed as possible additions to care rather than automatic natural remedies for PCOS. This distinction is particularly important when a supplement affects glucose, blood pressure or hormone levels. A product may be “natural” yet still produce pharmacological effects or interact with medicines. Before taking several products together, review the ingredients with a healthcare professional. This becomes especially important if you are pregnant, trying to conceive, breastfeeding or taking prescription medication.
Inositol
Strategy #9: Discuss inositol rather than assuming you need it. Inositol is one of the most studied supplements in PCOS and has attracted interest because of its possible relationship with insulin signaling and ovarian function. However, evidence does not justify presenting it as a guaranteed treatment. The international guideline describes the evidence around inositol for infertility outcomes as limited and uncertain.
Myo-Inositol and D-Chiro-Inositol
Myo-inositol and D-chiro-inositol are two forms commonly found in PCOS supplements. Many commercial products emphasize particular combinations or ratios. That marketing should not be mistaken for proof that one formulation is universally appropriate. Product quality, dose, treatment goal and individual circumstances all matter. Your clinician can help determine whether supplementation has a reasonable place in your personal care plan.
What Does the Research Say?
Current evidence does not support describing inositol as a proven fertility treatment for every person with PCOS. The international guideline states that benefits and risks remain too uncertain to recommend inositol as a fertility therapy and notes limited evidence for outcomes such as ovulation, clinical pregnancy and live birth.
Vitamin D
Vitamin D is essential for bone health and several physiological processes. Some people with PCOS also have low vitamin D levels, but that does not mean high-dose supplementation automatically improves PCOS outcomes. If deficiency is suspected or identified, testing and appropriate supplementation can be discussed with a healthcare professional. Avoid taking very high doses simply because a supplement is marketed for hormone balance.
Omega-3 Fatty Acids
Omega-3 fatty acids occur naturally in foods such as salmon, sardines and other fatty fish. They can also be obtained from certain supplements. Omega-3s are relevant to general cardiovascular and nutritional health, which matters because PCOS can occur alongside metabolic risk factors. However, an omega-3 supplement should not be presented as a replacement for diet, exercise or appropriate medical PCOS treatment.
Magnesium
Magnesium supplements may be useful when dietary intake is inadequate or a healthcare professional identifies a specific reason for supplementation. However, taking more is not necessarily better. Excess supplemental magnesium can cause gastrointestinal symptoms and may be inappropriate for some people. Food sources such as nuts, seeds, legumes and leafy greens remain practical ways to increase intake.
Zinc
Zinc is involved in immune function, cell processes and normal metabolism. It is sometimes included in PCOS supplements because of interest in acne, inflammation and androgen levels. However, evidence for zinc as a specific PCOS treatment remains limited. Excessive zinc can also interfere with copper status and cause other problems, so long-term high-dose use deserves professional guidance.
Chromium
Chromium has been studied because of its potential relationship with glucose metabolism and insulin sensitivity. Some research has suggested possible metabolic effects, but evidence is not strong enough to treat chromium as a standard PCOS therapy. If you are already taking medication that affects blood sugar, discuss chromium with your clinician before adding it.
Cinnamon
Cinnamon is a common food ingredient and has also been investigated in concentrated supplement form. Researchers have explored whether it might influence glucose regulation and some PCOS-related outcomes. Culinary use is very different from taking a high-dose extract. Concentrated products may have different safety considerations, so do not assume that more cinnamon means better results.
Berberine
Berberine has attracted considerable attention because of research involving glucose regulation, lipid metabolism and insulin resistance. However, evidence is mixed and much of the research concerns metabolic diseases rather than PCOS specifically. NCCIH notes gastrointestinal side effects and possible drug interactions and advises against berberine during pregnancy and breastfeeding because of potential risks.
Turmeric and Curcumin
Turmeric contains compounds including curcumin that have been studied for their biological and anti-inflammatory properties. Adding turmeric to food can be a simple culinary choice, but concentrated curcumin supplements are different. Their absorption, dose and formulation vary considerably. Evidence does not justify promising turmeric as a standalone treatment for PCOS hormone imbalance or fertility problems.
Calcium
Calcium is important for bones, muscles and normal physiological function. Most people should first consider whether their diet provides adequate calcium through foods such as dairy products or fortified alternatives. A supplement may be appropriate in certain circumstances, but unnecessary high intake is not automatically beneficial for PCOS. Your nutritional needs should guide supplementation.
Evening Primrose Oil
Evening primrose oil is often marketed for women’s hormonal health, but evidence for meaningful PCOS-specific benefits is limited. It should therefore remain a cautious consideration rather than a central part of natural PCOS treatment. If you are taking medication or preparing for pregnancy, discuss its use with a healthcare professional before starting it.
What to Know Before Taking Supplements
Strategy #10: Evaluate the product before taking it. Look at the ingredients, dose, intended purpose, evidence and possible interactions. Two bottles with similar labels may contain very different formulations. NCCIH notes that supplements sold to consumers can differ from products used in research and that evidence varies widely between ingredients.
Possible Drug Interactions and Side Effects
Supplements can cause side effects or interact with medicines. This includes products that affect glucose, blood pressure, clotting or hormone levels. Contamination and inaccurate labeling are additional concerns. These risks become more important when several dietary supplements are combined. Tell your healthcare providers about every supplement you use rather than assuming they are irrelevant to your medical record.
3. Consider Herbal and Complementary Approaches
Herbal products occupy a complicated space in alternative PCOS therapies. Some have traditional histories and small clinical studies, while others have little meaningful evidence in PCOS. This does not mean every herb is useless. It means you should separate traditional use, laboratory research and human clinical evidence. Those three things are not interchangeable.
A particularly important issue is safety. Herbal supplements can affect medication metabolism, blood pressure, glucose or other biological pathways. NCCIH emphasizes that safety information varies considerably and that manufacturers do not have to establish the same evidence of effectiveness required for approved drugs before dietary supplements reach consumers.
Spearmint Tea
Strategy #11: Consider spearmint tea as a modest complementary option. Small studies have investigated spearmint in relation to androgen-related symptoms, but the evidence is not strong enough to treat it as a replacement for established care. If you enjoy the tea and tolerate it well, it can be part of a healthy routine. Keep expectations realistic rather than expecting dramatic changes in androgen activity.
Cinnamon and Herbal Preparations
Cinnamon can be used as a food or concentrated supplement. Food-level use is generally straightforward, while herbal preparations may deliver substantially larger amounts. Because concentrated products differ in formulation, their effects and risks may also differ. The same principle applies to many adaptogen herbs and botanical blends marketed for hormone regulation.
Chasteberry
Chasteberry has a long history of traditional use for menstrual and reproductive concerns. However, traditional use does not establish that it effectively treats PCOS. If you are considering it for cycle symptoms or fertility, discuss the product with a healthcare professional. This is especially important when other hormone-related medicines are involved.
Ashwagandha
Ashwagandha is often marketed for stress, sleep and hormonal wellness. NCCIH reports that evidence is clearer for some short-term stress and insomnia outcomes than for female fertility or other conditions. Safety also matters because reported concerns include gastrointestinal effects, rare liver injury and interactions with several medicines. It should be avoided during pregnancy and breastfeeding.
Maca Root
Maca root is frequently promoted for energy, libido and reproductive wellness. Yet evidence for treating PCOS itself remains limited. Marketing claims can easily outrun clinical research. If you are considering maca for fertility or ovulation, treat it as an unproven complementary option rather than assuming it can correct an underlying PCOS hormone imbalance.
Holy Basil
Holy basil, also known as tulsi, is traditionally used in several wellness systems. Modern interest includes stress and metabolic health. However, evidence specifically supporting holy basil as a PCOS therapy is not robust. If you choose an herbal product, consider the complete formulation rather than focusing only on one attractive ingredient printed on the front of the bottle.
Licorice Root
Licorice root deserves particular caution. It contains glycyrrhizin, which can produce important effects on blood pressure, potassium and cardiovascular function when consumed in significant amounts. NCCIH reports potentially serious adverse effects with excessive or prolonged intake. People with hypertension, heart or kidney problems need particular caution.
Tribulus Terrestris
Tribulus terrestris is another botanical frequently included in discussions about reproductive health and PCOS. Human evidence remains limited and does not establish it as a reliable treatment. If a supplement promises to “balance hormones” or restore fertility quickly, examine the claim carefully. Strong language in advertising is not a substitute for strong clinical evidence.
Why “Natural” Does Not Always Mean Safe
Strategy #12: Treat natural products with the same seriousness as other active substances. Herbs can contain biologically active compounds that affect the body. They can also interact with medicines or cause adverse effects. NCCIH specifically warns that “natural” does not necessarily mean safe and recommends discussing complementary products with healthcare professionals.
Quality and Dosage Matter
The dose used in a study may not match the amount found in a commercial product. Extracts, teas, capsules and combination formulas can have different concentrations. Some products also contain multiple ingredients, making it difficult to know which component causes an effect. Look for transparent labeling and appropriate quality controls rather than relying solely on impressive marketing terms.
When to Avoid Herbal Supplements
Extra caution is appropriate during pregnancy, breastfeeding, before surgery or when taking prescription medicines. The same applies when you have liver, kidney, thyroid, cardiovascular or other significant health conditions. For example, NCCIH warns about several important safety issues involving ashwagandha, berberine and licorice root.
4. Move Your Body in a Way You Can Maintain
Physical activity is one of the most practical PCOS lifestyle changes because it can support metabolic health, fitness, mood and quality of life. Importantly, the goal does not have to be rapid weight loss. The international guideline recommends sustainable physical activity according to individual preferences and emphasizes that no single exercise type is universally superior for PCOS.
That flexibility matters. You do not need a perfect gym routine to benefit from movement. Walking, resistance exercise, cycling, swimming, yoga, Pilates and other activities can all have a place. The best routine is usually one you can continue when work becomes busy, motivation dips or life gets messy.
Combine Aerobic Exercise With Strength Training
Strategy #13: Combine aerobic activity with muscle strengthening. Aerobic exercise can improve cardiovascular fitness while resistance work challenges muscles and supports physical function. You might combine brisk walking with bodyweight exercises or cycling with resistance bands. The objective is not to create an exhausting routine. It is to develop a balanced pattern of regular exercise that fits your life.
Try Resistance Training for Metabolic Health
Strategy #14: Include resistance training. Weight machines, resistance bands, free weights and bodyweight exercises can all strengthen muscles. Building strength can also make everyday activities easier. Start with manageable loads and gradually increase difficulty. You do not need advanced bodybuilding techniques to make resistance exercise a useful part of your PCOS treatment plan.
Walking Can Be a Simple Starting Point
Strategy #15: Walk more often. Walking is accessible, inexpensive and easy to scale. A short walk after meals or regular movement breaks during sedentary work can increase your overall activity. You can start with a comfortable pace and build gradually. If you currently exercise very little, consistency is more valuable than trying to imitate an extreme online fitness program.
Consider Yoga, Pilates, or Low-Impact Exercise
Strategy #16: Choose movement you enjoy.Yoga, Pilates and swimming can provide physical activity without requiring high-impact training. Aerobics can also work if you enjoy group exercise. The right activity depends on your fitness level, preferences and physical limitations. Enjoyment matters because a routine you willingly repeat is more useful than a theoretically perfect program you quickly abandon.
Avoid Overtraining and Extreme Exercise
More exercise is not automatically better. Very demanding routines can become difficult to recover from, particularly when combined with inadequate nutrition or poor sleep. High-intensity interval training and long-distance running can be appropriate for some people, but they are not requirements for PCOS. Your program should challenge you without becoming an unsustainable source of physical or psychological stress.
How Often Should You Exercise With PCOS?
For adults, the international PCOS guideline aligns with general activity recommendations that include around 150–300 minutes of moderate-intensity activity or 75–150 minutes of vigorous activity each week, alongside muscle-strengthening activity on at least two non-consecutive days. Your starting point can be lower if needed. Progress gradually rather than treating the target as an all-or-nothing rule.
Make Movement Part of Your Daily Routine
Strategy #17: Reduce prolonged sitting. Take short movement breaks, walk while making phone calls, use stairs when practical or add brief activity between tasks. These small changes may seem insignificant individually, but they can accumulate. Think of daily movement as a background habit rather than something that only happens when you put on workout clothes.
5. Support a Healthy Weight and Metabolic Health
PCOS and metabolism are closely connected, but weight should never become the only measure of health. Insulin resistance, glucose abnormalities, blood pressure and lipid changes can occur alongside PCOS. The international guideline states that people with PCOS have increased risks of impaired glucose regulation and type 2 diabetes regardless of age or BMI. (ASRM)
A healthy weight can be an appropriate goal for some people, but health exists across a range of body sizes. Sustainable nutrition, movement, sleep and metabolic monitoring can be valuable regardless of whether the scale changes dramatically. A compassionate approach is often more productive than repeated cycles of restriction and regain.
Understand the Connection Between PCOS and Insulin Resistance
Insulin resistance means the body’s cells respond less effectively to insulin, which can contribute to changes in insulin metabolism and glucose regulation. PCOS is not simply an insulin disorder, however. Hormonal, reproductive and metabolic pathways interact in complicated ways. Understanding this connection can help you make informed choices without reducing every PCOS symptom to blood sugar alone.
Focus on Sustainable Habits Rather Than Crash Diets
Strategy #18: Avoid crash diets. A very restrictive low-calorie diet may produce short-term weight changes, but it can be difficult to maintain and may create an unhealthy relationship with food. A sustainable eating pattern is usually more practical. Focus on meals you can repeat, enjoyable foods and gradual improvements rather than dramatic promises about rapid weight management.
Set Realistic, Individualized Health Goals
Your goals might involve more predictable periods, better fitness, improved sleep, healthier metabolic markers or support for fertility. Weight loss may be relevant for some people, but it does not need to define every treatment goal. A personalized plan also allows you to account for age, medications, pregnancy plans, cultural foods, physical ability and your current level of activity.
Why Weight Is Not the Only Measure of PCOS Health
The scale cannot measure everything that matters. Menstrual cycle patterns, blood pressure, glucose status, cholesterol, physical fitness, acne, excess hair growth, sleep and emotional well-being can all provide useful information. Someone may improve metabolic health without dramatic weight change. That is why PCOS management should consider the whole person rather than turning one measurement into the entire story.
PCOS Can Affect People at Different Body Sizes
PCOS is not restricted to people with obesity or a higher body weight. People with different body sizes can experience PCOS symptoms, including menstrual irregularity, androgen-related symptoms and metabolic abnormalities. Weight stigma can also discourage people from seeking care. A respectful approach focuses on symptoms, risks and individual health needs rather than making assumptions based solely on appearance.
Monitor Blood Sugar, Cholesterol, and Other Metabolic Risk Factors
Strategy #19: Monitor metabolic health. The international guideline recommends assessing glycemic status at PCOS diagnosis because the condition is associated with increased risk of impaired glucose tolerance and type 2 diabetes. Cardiovascular risk factors also deserve attention. Depending on your situation, your clinician may assess glucose, lipids, blood pressure and other relevant markers over time.
6. Improve Sleep and Manage Stress
Sleep and stress are easy to overlook when discussing natural PCOS treatment, yet they influence everyday behavior, energy and quality of life. Poor sleep can make exercise harder and may affect food choices and emotional well-being. Meanwhile, ongoing stress can make it difficult to maintain routines. Improving these areas does not “reset” your hormones overnight, but it can strengthen the foundation of long-term self-care.
Your goal is not perfect relaxation. Instead, create a realistic system that helps you recover. Consistent sleep, calming evening habits, enjoyable movement and practical stress management can become part of your broader approach to hormone balance and well-being. If symptoms suggest a sleep disorder, however, lifestyle measures alone may not be enough.
Build Better Sleep Habits
Strategy #20: Strengthen your sleep hygiene. Aim for a regular sleep schedule and create an environment that supports rest. Keep your bedroom comfortable and reduce activities that make it difficult to wind down. Good sleep habits are not glamorous, but they are often easier to maintain than complicated wellness routines that promise dramatic hormonal changes.
Keep a Consistent Sleep Schedule
Going to bed and waking at roughly consistent times can provide structure for your sleep pattern. Your exact schedule depends on work, family responsibilities and personal needs. The important point is regularity. If your sleep varies dramatically between weekdays and weekends, gradually moving toward greater consistency may be more realistic than trying to change everything in one night.
Create a Relaxing Bedtime Routine
Strategy #21: Develop a calming pre-sleep ritual. Dim bright lights, reduce stimulating activities and choose quiet habits such as reading or gentle stretching. If screens keep you mentally engaged, create a period without them before bed. These steps are simple forms of self-care and relaxation, not magical PCOS treatments. Their value comes from supporting healthier sleep behavior.
Screen for Sleep Problems When Necessary
PCOS is associated with an increased risk of obstructive sleep apnea, particularly when other risk factors are present. Persistent loud snoring, witnessed breathing pauses, morning headaches or excessive daytime sleepiness deserve medical attention. If you have ongoing sleep disturbances, do not assume they are simply caused by stress. Identifying a genuine sleep disorder can be an important part of comprehensive care.
Practice Stress-Management Techniques
Strategy #22: Make stress management practical. A short walk, conversation with someone you trust, breathing practice, enjoyable hobby or regular downtime may help. Stress does not have one universal cause or solution. Rather than chasing a perfect cortisol levels routine, identify activities that genuinely help you recover and that you can repeat during demanding periods.
Try Mindfulness, Meditation, or Breathing Exercises
Mindfulness and breathing exercises can provide simple ways to create a pause during stressful moments. They may help some people feel calmer, although they should not be promoted as direct cures for PCOS hormone imbalance. The benefit is often behavioral and psychological: when you feel more regulated, maintaining healthy routines can become easier.
Consider Yoga for Stress and Well-Being
Yoga combines movement, balance and relaxation practices. It can therefore fit naturally into a lifestyle plan that addresses both physical activity and stress. The goal should be improved well-being rather than the promise that yoga will normalize every hormone. If you enjoy it, yoga can become one component of sustainable PCOS lifestyle changes.
Understand the PCOS–Stress–Sleep Connection
PCOS symptoms can create stress, while stress and poor sleep can make healthy routines harder to maintain. This can become a frustrating cycle. You might sleep poorly because you feel anxious about symptoms, then struggle with energy the following day. Breaking the cycle does not require perfection. Small improvements in sleep, movement, nutrition and stress management can reinforce one another.
7. Consider Environmental and Complementary Therapies
Some approaches to PCOS focus on environmental exposures or complementary medicine. These areas are interesting but require careful interpretation. Research into endocrine disruptors, the gut microbiome and complementary therapies continues to evolve. Association does not automatically mean causation, and reducing an exposure where practical is different from claiming that exposure caused your PCOS.
This section is therefore about sensible risk reduction rather than fear. You do not need to turn your home into a laboratory or eliminate every chemical mentioned online. Similarly, acupuncture, probiotics and microbiome products should not be presented as proven replacements for established care. The evidence should determine how confidently each approach is described.
Reduce Exposure to Potential Endocrine Disruptors
Strategy #23: Reduce unnecessary exposure to potential endocrine disruptors where practical. Researchers have investigated substances such as BPA, phthalates, certain pesticides and other chemicals because of their possible effects on the endocrine system. However, everyday exposure does not prove that a person will develop PCOS. Reasonable exposure reduction can be considered without adopting extreme avoidance behaviors.
Common Sources of Endocrine-Disrupting Chemicals
Potential sources discussed in environmental health research include some plastics, food packaging, cosmetics and household products. Examples may include BPA, phthalates, dioxins, certain pesticides and some glycol ethers. The presence of a chemical in a product does not automatically indicate dangerous exposure. Risk depends on factors such as dose, duration and route of exposure.
Practical Ways to Reduce Everyday Exposure
If you want to reduce exposure, focus on practical habits rather than perfection. Follow food-storage guidance, avoid heating food in containers not designed for that purpose and wash produce appropriately. Consider reducing unnecessary use of strongly fragranced products if that fits your preferences. These steps may reduce certain exposures without creating anxiety around ordinary daily life.
What Does Acupuncture Have to Do With PCOS?
Strategy #24: View acupuncture as a complementary therapy rather than a replacement treatment. Acupuncture has been studied in PCOS for outcomes including menstrual patterns, metabolic measures and reproductive function. Research findings are not strong enough to present acupuncture as a universal PCOS therapy. If you use it, choose a qualified practitioner and continue appropriate medical monitoring.
Consider Probiotics and Gut Health
Strategy #25: Support gut health through overall diet before relying on supplements. Foods such as kombucha, kimchi, yogurt and other fermented foods can fit into a varied eating pattern when tolerated. Probiotics are also available as supplements, but different strains can have different effects. A product that helps one condition cannot automatically be assumed to treat PCOS.
The Gut Microbiome and PCOS
Researchers are investigating relationships between the gut microbiome, metabolism, inflammation and reproductive health. This has created considerable interest in the possibility that gut bacteria could influence aspects of PCOS. However, microbiome research is still developing. It would be premature to claim that changing your gut bacteria can reliably correct hormone regulation, insulin resistance or ovulation.
What the Evidence Actually Shows
The evidence around probiotics and PCOS remains variable because studies use different strains, doses, diets and populations. Some research reports potentially beneficial metabolic or inflammatory effects, but that does not establish a single probiotic as standard PCOS treatment. For now, a diverse nutrient-rich diet is a more established foundation than relying on one commercial microbiome product.
Track Your Menstrual Cycle and Symptoms
Strategy #26: Track your menstrual cycle. Record period dates, bleeding patterns, acne, hair growth, pain, sleep and other symptoms. Tracking can help you notice changes and provide useful information during medical appointments. It can also make fertility planning more informed because changes in cycle patterns may provide clues about ovulation, although tracking alone cannot confirm ovulation.
Identify Your Personal PCOS Triggers
Strategy #27: Look for individual patterns without assuming every symptom has one cause. You may notice that poor sleep, stress, certain foods or disrupted routines coincide with changes in symptoms. Tracking can help you discuss these observations with a professional. Avoid unnecessarily eliminating foods based on online claims unless there is a clear medical or personal reason.
Build a Consistent Daily Routine
Strategy #28: Build consistency rather than chasing perfection. A practical routine might include regular meals, movement, adequate sleep, symptom tracking and planned healthcare appointments. Consistency helps turn individual healthy behaviors into habits. You do not need to follow a flawless wellness schedule every day. A routine that survives busy weeks is usually more useful than an ideal routine that lasts five days.
8. Know When Natural PCOS Management Is Not Enough
Natural strategies can be valuable, but PCOS is a long-term endocrine and reproductive condition that sometimes requires medical treatment. A healthy lifestyle cannot replace evaluation when symptoms are severe or persistent. Irregular periods, fertility problems, heavy bleeding and significant metabolic abnormalities all deserve appropriate attention.
The key is not choosing between natural care and medical care. Good management can include both. Nutrition, exercise, sleep and stress management may sit alongside medication, fertility treatment or other interventions when clinically appropriate. The international guideline emphasizes individualized care and ongoing assessment because PCOS affects different people in different ways.
Talk With Your Doctor Before Starting Supplements
Strategy #29: Discuss supplements before using them. This is especially important when taking several products at once. Tell your clinician about inositol, vitamins, minerals, herbs and combination formulas. Mention pregnancy plans and prescription medicines. A professional can help you distinguish a reasonable nutritional supplement from a product with uncertain benefits or unnecessary risks.
When Irregular Periods Need Medical Evaluation
Persistent irregular periods should not simply be accepted as an unavoidable part of PCOS. Long gaps between periods can have implications for the uterine lining. Your clinician can determine whether treatment is needed to regulate bleeding or protect the endometrium. Do not rely solely on teas, supplements or lifestyle changes when menstrual irregularity is persistent.
When to Seek Help for Fertility Problems
If pregnancy is your goal and conception is taking longer than expected, professional assessment can be valuable. PCOS can interfere with regular ovulation, but effective fertility treatments are available. PCOS fertility support may include lifestyle measures, ovulation-inducing medicines and other approaches depending on your circumstances. Natural approaches should not delay appropriate fertility evaluation when it is needed.
Don’t Ignore Heavy or Unusual Bleeding
Very heavy, prolonged or unusual bleeding deserves medical evaluation. Do not assume that severe bleeding is simply another PCOS symptom. Depending on the cause, significant blood loss can contribute to iron deficiency or anemia. Urgent symptoms such as severe bleeding accompanied by dizziness, fainting or significant weakness require prompt medical attention.
Managing Excess Hair Growth and Acne
Excess facial or body hair and acne can be emotionally difficult as well as physically noticeable. These symptoms can be associated with elevated androgen levels or increased sensitivity to male sex hormones. Lifestyle changes may support general health but may not fully address these symptoms. Dermatological and hormonal treatments can provide additional options when appropriate.
Why PCOS Should Be Monitored Long Term
PCOS deserves long-term attention because its effects can extend beyond reproductive symptoms. The condition is associated with increased risks involving glucose regulation, cardiovascular risk factors and endometrial health. Regular monitoring allows problems to be identified earlier and gives you a chance to adjust your care plan as your needs change.
Blood Sugar and Diabetes Risk
People with PCOS have increased risks of impaired fasting glucose, impaired glucose tolerance and type 2 diabetes regardless of age or BMI. The international guideline recommends assessing glycemic status at diagnosis. Your clinician can determine which test and follow-up schedule is appropriate for you.
Cholesterol and Cardiovascular Health
PCOS management should also consider cardiovascular risk factors. Blood pressure, lipid levels, glucose status, physical activity, smoking status and other factors may contribute to overall risk. A healthy lifestyle can support cardiovascular health, but monitoring remains important. You should not assume that feeling well means metabolic markers are automatically normal.
Endometrial Health
Long-standing untreated absence of menstrual bleeding can increase the risk of endometrial hyperplasia in people with PCOS. The international guideline notes that premenopausal people with PCOS have a substantially higher risk of endometrial hyperplasia and endometrial cancer, although the overall absolute risk of endometrial cancer remains low. Cycle regulation and appropriate progestin or other medical management may sometimes be necessary.
Natural Approaches Should Complement, Not Replace, Medical Care
Natural approaches can form an important part of a broader management strategy, but they should complement rather than replace appropriate PCOS treatment. Be cautious about anyone promising a guaranteed cure through herbs, supplements, systemic enzyme therapies or one restrictive diet. PCOS is complex, and effective care should reflect your symptoms, reproductive goals, metabolic health and personal preferences.
Questions to Ask Your Doctor About PCOS
Strategy #30: Become an active participant in your care. Ask which symptoms require evaluation, whether your blood sugar and cholesterol need monitoring, whether your menstrual pattern needs treatment and which supplements are appropriate. If fertility is a priority, ask how ovulation can be assessed and what evidence-based options are available. Good questions can turn a confusing diagnosis into a clearer long-term plan.
Natural PCOS Management: What Matters Most?
There is no single magic ingredient hiding at the bottom of a supplement bottle. The most useful approach is usually a combination of sustainable habits, appropriate monitoring and individualized medical care. A balanced PCOS diet, regular exercise, adequate sleep and practical stress management can provide a strong foundation.
Supplements and herbal supplements may deserve discussion in selected situations, but their evidence varies considerably. Products such as inositol, berberine, vitamin D, omega-3 fatty acids, cinnamon and various herbs should not all be placed in the same evidence category. Some have more research than others, while several popular remedies remain uncertain.
Evidence & Efficacy Guide
PCOS Management Approaches Compared
Explore evidence-based lifestyle changes, dietary strategies, and supplements for managing PCOS symptoms.
Approach
Main Reason People Consider It
Evidence Perspective
Balanced Eating Pattern
Lifestyle
Metabolic and overall health
Strong FoundationLifestyle management base
Regular Physical Activity
Lifestyle
Fitness and metabolic health
Strong FoundationLifestyle management base
Weight Management
(when appropriate)Lifestyle
Metabolic and reproductive health
IndividualizedTailored to individual goals
Sleep Improvement
Lifestyle
Well-being and symptom management
SupportiveImportant supportive strategy
Stress Management
Lifestyle
Quality of life and healthy routines
SupportiveUseful supportive strategy
Inositol
Supplement
Insulin signaling and reproductive outcomes
InconsistentEvidence remains uncertain for several outcomes
Vitamin D
Supplement
Correcting deficiency
TargetedAppropriate when deficiency exists
Omega-3 Fatty Acids
Supplement
General nutritional and cardiovascular health
VariablePCOS-specific effects vary
Berberine
Supplement
Glucose and metabolic effects
PromisingSafety and evidence limitations matter
Probiotics
Supplement
Gut and metabolic health
DevelopingResearch is still developing
Herbal Products
Herbal
Various traditional or marketed benefits
VariableEvidence varies widely
Acupuncture
Therapy
Complementary symptom management
MixedEvidence remains mixed
The most important takeaway is simple: natural does not mean automatically effective and medical does not mean incompatible with healthy lifestyle care. You can eat nourishing foods, move your body, improve sleep and manage stress while also receiving appropriate medical treatment. That balanced approach gives you more tools without forcing you to choose between wellness and evidence-based healthcare. If you are living with Polycystic ovary syndrome, start with changes you can realistically maintain. One nutritious meal is better than an unsustainable diet. One walk is better than an abandoned workout plan. One useful conversation with your clinician can be more valuable than a cupboard full of unproven supplements. Over time, these small decisions can become a practical and personalized strategy for managing PCOS.